

Quick answer: Raynauds Syndrome When Your Toes Hands Or Feet Turn Red Or White is a clinical condition that responds to evidence-based treatment when caught early. Symptoms include pain, swelling, and altered function. Diagnosis requires clinical exam, often imaging. Treatment ladder: conservative care first (4-6 weeks), then targeted interventions if needed. Call (810) 206-1402.
Medically reviewed by Dr. Tom Biernacki, DPM · Board-Certified Podiatric Surgeon · Last reviewed: April 2026 · Editorial Policy
The most important clinical decision with Raynauds Syndrome When Your Toes Hands Or Feet Turn Red Or White isn’t which treatment to start with — it’s identifying the correct subtype. That changes everything. Call (810) 206-1402.
Quick Answer
Raynaud’s Syndrome 2026: When Toes Turn White, Blue &# relates to toe deformity — typically caused by imbalanced muscles + footwear. Most patients improve in depends on severity with conservative care. Same-week appointments in Howell + Bloomfield Township: (810) 206-1402.

Medically Reviewed by Dr. Daria Gutkin, DPM — Board-Qualified Podiatric Physician
Balance Foot & Ankle, Michigan · Updated April 2026
⚡ Quick Answer
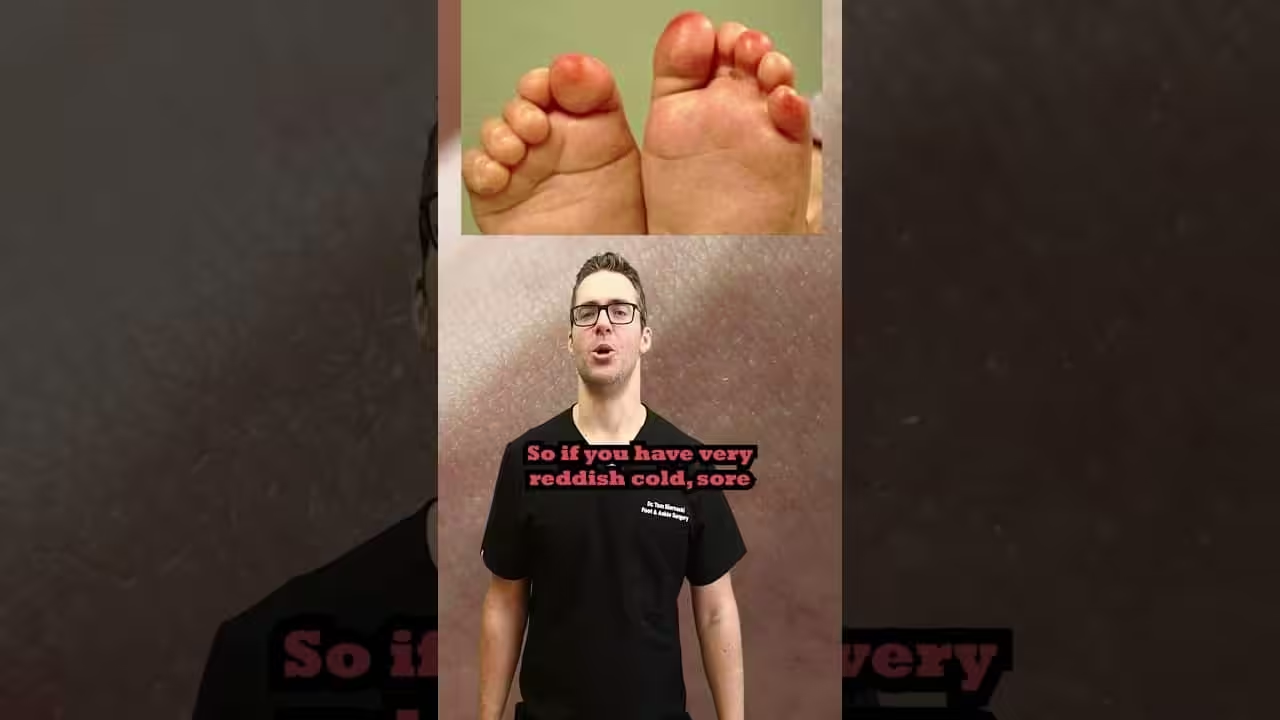
Raynaud’s syndrome (also called Raynaud’s phenomenon or Raynaud’s disease) causes the small blood vessels in the fingers and toes to overreact to cold temperatures or stress, dramatically reducing blood flow. The classic presentation is a three-phase color change: white (loss of blood flow) → blue (deoxygenated blood) → red (blood flow returns with painful throbbing). Raynaud’s affects approximately 5–10% of the general population, with women 5–9 times more likely to be affected than men. Primary Raynaud’s is typically harmless and manageable with lifestyle changes, while secondary Raynaud’s (caused by an underlying autoimmune condition) may require medication and closer monitoring.
Your toes turn ghost-white during a winter walk, then shift to a disturbing shade of blue while you’re warming up inside, and finally flush bright red with a painful throbbing sensation. This dramatic color sequence isn’t just poor circulation — it’s Raynaud’s syndrome, and for millions of people living in cold climates like Michigan, it can be a daily challenge from October through April.
At Balance Foot & Ankle, we evaluate patients with cold, discolored toes regularly — and an important part of that evaluation is distinguishing Raynaud’s from other causes of cold feet, poor circulation, and color changes that may signal more serious conditions. Here’s what you need to know about why it happens, whether it’s dangerous, and how to manage it effectively.
Primary vs. Secondary Raynaud’s
| Feature | Primary Raynaud’s (~80% of cases) | Secondary Raynaud’s (~20% of cases) |
|---|---|---|
| Also Called | Raynaud’s disease | Raynaud’s phenomenon |
| Age of Onset | Teens to 20s | Typically after age 30 |
| Underlying Cause | None identified; exaggerated vascular response | Associated autoimmune disease, vascular disease, or medication |
| Severity | Mild to moderate; symmetrical; no tissue damage | Can be severe; may cause ulcers, tissue loss |
| Blood Tests | Normal | ANA, ESR, anti-centromere antibodies may be positive |
| Prognosis | Benign; may improve with age | Depends on underlying condition; requires ongoing management |
What Causes Raynaud’s?
In healthy blood vessels, cold exposure causes mild, gradual vasoconstriction — a normal response to conserve body heat. In Raynaud’s, the blood vessels (primarily the small arterioles in the fingers and toes) go into severe vasospasm, almost completely shutting off blood flow for minutes to hours.
Primary Raynaud’s Triggers
Cold temperature is the most common trigger — even brief exposure like reaching into a freezer, holding a cold drink, or walking in cool weather. Emotional stress can trigger episodes independently of temperature because the same sympathetic nervous system pathways control both the stress response and blood vessel constriction. Hormonal factors play a role, which explains the strong female predominance. Genetic predisposition is significant — roughly 1 in 4 people with Raynaud’s have a first-degree relative with the condition.
Secondary Raynaud’s Causes
Autoimmune diseases — Scleroderma is the most common association (90% of scleroderma patients have Raynaud’s). Lupus, rheumatoid arthritis, Sjögren’s syndrome, and dermatomyositis are also frequently linked. These conditions damage the blood vessel walls directly.
Peripheral artery disease — Atherosclerosis narrows the arteries feeding the feet, compounding the vasospasm effect. Patients with PAD and Raynaud’s are at higher risk of tissue complications.
Medications — Beta-blockers (metoprolol, atenolol), certain migraine medications (ergotamine), ADHD stimulants, decongestants (pseudoephedrine), and some chemotherapy drugs can trigger or worsen Raynaud’s.
Occupational factors — Repetitive vibrating tool use (vibration white finger), frostbite history, and chemical exposure (vinyl chloride) can cause secondary Raynaud’s in the affected extremities.
⚠️ When Raynaud’s Needs Urgent Evaluation
- Toes or fingers that stay blue/white for more than 30 minutes despite warming efforts
- Open sores or ulcers developing on the fingertips or toes — suggests tissue damage from severe ischemia
- Asymmetric symptoms (affecting one foot but not the other) — may indicate vascular disease rather than Raynaud’s
- Raynaud’s starting after age 30 without prior history — higher likelihood of secondary cause
- Associated symptoms: joint pain, skin thickening, mouth sores, unexplained rash, or difficulty swallowing (may suggest autoimmune disease)
The Three Phases of a Raynaud’s Attack
Phase 1 — White (Pallor): Blood vessels spasm shut. Affected toes or fingers turn white and feel cold and numb. This is the ischemic phase — tissue is temporarily deprived of oxygen.
Phase 2 — Blue (Cyanosis): As remaining blood in the tissues loses oxygen, the toes turn blue or purple. This phase often occurs as the tissue begins to warm up. Tingling or pins-and-needles sensations are common.
Phase 3 — Red (Rubor): As blood vessels reopen, blood rushes back into the tissues. Toes turn bright red, feel warm, and may throb or swell. This reperfusion phase can be the most painful part of the attack.
Not everyone experiences all three phases — some patients only go through two, and the attack pattern can vary between episodes. Duration ranges from a few minutes to several hours in severe cases.
Raynaud’s in the Feet vs. Hands
While Raynaud’s is most commonly discussed in terms of finger involvement, the toes are affected in approximately 40% of cases — and in some patients, the feet are the primary site. Foot involvement presents unique challenges because the feet are naturally farther from the heart (longer distance for blood to travel), shoes and socks create a closed environment that can trap moisture and cold, and standing and walking compress the small arteries of the foot.
As podiatrists, we pay particular attention to foot-specific Raynaud’s because the consequences of tissue ischemia in the feet — ulcers, infection, delayed wound healing — are compounded by weight-bearing demands and are more difficult to treat than fingertip complications.
Diagnosis
Raynaud’s is primarily diagnosed clinically — the characteristic color changes (especially the white phase) with cold exposure are highly specific. Your doctor may use a cold stimulation test (immersing the hands or feet in cold water and monitoring color changes and recovery time) to confirm the diagnosis.
For suspected secondary Raynaud’s, blood tests include ANA (antinuclear antibody), ESR/CRP (inflammation markers), anti-centromere and anti-Scl-70 antibodies (scleroderma markers), complement levels, and a complete blood count. Nailfold capillaroscopy — a painless microscopic examination of the tiny blood vessels at the base of the fingernails — is one of the most useful tests for distinguishing primary from secondary Raynaud’s. Abnormal capillary patterns strongly suggest an underlying autoimmune condition.
Treatment and Management
Lifestyle Strategies (First-Line for All Patients)
Layer and insulate — Wear moisture-wicking socks as a base layer, followed by wool or synthetic insulating socks. Keep your core warm (a warm core means less vasoconstriction in the extremities) with layered clothing, a warm hat, and gloves. Chemical or battery-powered hand and toe warmers are invaluable for Michigan winters.
Avoid rapid temperature changes — Transition gradually between temperatures. Use insulated bags for frozen groceries. Warm your car before getting in. Avoid holding cold drinks directly — use insulated sleeves.
Exercise regularly — Cardiovascular exercise improves overall circulation and can reduce the frequency and severity of Raynaud’s attacks. Aim for 30 minutes of moderate activity most days.
Quit smoking — Nicotine is a powerful vasoconstrictor that directly worsens Raynaud’s. Smoking cessation can be one of the most impactful interventions.
Manage stress — Stress-triggered Raynaud’s responds well to relaxation techniques including deep breathing, progressive muscle relaxation, and biofeedback (which has specifically been studied for Raynaud’s with positive results).
Medications (For Moderate-to-Severe Cases)
| Medication | How It Works | Key Notes |
|---|---|---|
| Nifedipine (calcium channel blocker) | Relaxes blood vessel walls; most-studied Raynaud’s medication | First-line Rx; reduces attack frequency by ~50%; may cause headache, ankle swelling |
| Amlodipine (calcium channel blocker) | Similar mechanism to nifedipine with longer duration | Better tolerated; once-daily dosing; fewer headaches |
| Sildenafil (PDE5 inhibitor) | Dilates blood vessels via nitric oxide pathway | Used for severe or refractory cases; particularly helpful for digital ulcers |
| Topical nitroglycerin | Applied directly to affected digits; local vasodilation | Useful for targeted treatment; headache common side effect |
| Losartan (ARB) | Blocks angiotensin receptor; mild vasodilatory effect | Some evidence; dual benefit for blood pressure; well-tolerated |
Footwear for Raynaud’s
The right footwear is critical for managing foot-specific Raynaud’s. Prioritize insulation (lined boots in winter), moisture-wicking (wet feet lose heat rapidly), a roomy fit (tight shoes compress blood vessels and worsen ischemia), and avoid constricting socks or elastic bands around the ankles.
Products That Help Manage Raynaud’s in Feet
We may earn a commission through affiliate links below — but every product is independently selected and recommended based on clinical experience. This does not affect our recommendations.
🏆 #1 Pick — Hoka Bondi 8
The Bondi’s thick EVA midsole acts as insulation between your foot and cold ground surfaces — a significant factor in triggering Raynaud’s attacks during walking. The roomy toe box prevents compression of the small blood vessels in the toes, and the wide fit accommodates layered socks without creating constriction. This is the daily shoe we recommend most for Raynaud’s patients who need to stay active year-round.
Danner Bull Run Work Boots
For cold-weather protection, Danner’s insulated leather boots with Vibram outsoles provide excellent thermal protection while maintaining the roomy fit Raynaud’s patients need. The full-grain leather blocks wind, the insulation traps body heat, and the cushy footbed provides comfort for all-day wear. A premium choice for patients who work outdoors or need winter protection beyond what athletic shoes can provide.
Oofos OOahh Recovery Slides
For indoor use, Oofos’ foam recovery slides keep your feet off cold floors — one of the most common Raynaud’s triggers at home. The closed-cell foam insulates from ground temperature and the arch support maintains healthy circulation. Use these as indoor house shoes year-round instead of walking barefoot on tile or hardwood.
In-Office Treatment at Balance Foot & Ankle
If home treatment isn’t providing relief for your foot and ankle conditions, our podiatry team at Balance Foot & Ankle can help with same-day evaluations and advanced in-office care.
Same-day appointments available. (810) 206-1402
Frequently Asked Questions
Primary Raynaud’s (the most common type, affecting about 80% of patients) is not serious — it’s uncomfortable and inconvenient but doesn’t cause lasting tissue damage. Secondary Raynaud’s, caused by an underlying autoimmune condition like scleroderma, can be more serious because the prolonged reduced blood flow may lead to skin ulcers, tissue loss, or in rare severe cases, gangrene. The key is distinguishing between the two types, which your doctor can do through blood tests and clinical evaluation.
Cold temperature is the most common trigger — even mild exposure like air conditioning or reaching into a refrigerator can provoke an episode. Emotional stress activates the same sympathetic nervous system pathways and can trigger attacks independently of temperature. Other triggers include smoking, caffeine, certain medications (beta-blockers, decongestants), vibrating tools, and rapid temperature changes. Many patients find that keeping their core body warm (not just their hands and feet) is one of the most effective prevention strategies.
Primary Raynaud’s cannot be cured, but it can be effectively managed with lifestyle modifications and, when needed, medications. Many patients find their symptoms improve with age. Secondary Raynaud’s may improve if the underlying condition (such as an autoimmune disease) is well-controlled. The goal of treatment isn’t cure but rather reducing the frequency, duration, and severity of attacks and preventing tissue complications.
The hallmark of Raynaud’s is the distinctive color change — toes turning clearly white (blanching), then blue, then red. General poor circulation from peripheral artery disease causes the toes to feel cool and may cause a dusky or pale appearance, but not the dramatic white-blue-red sequence. Raynaud’s episodes are triggered by cold or stress and resolve with warming, while PAD symptoms are more related to walking distance and activity. Both conditions can coexist, so if you’re experiencing cold, discolored toes, a podiatric evaluation can determine the cause and whether vascular testing is needed.
The Bottom Line
Raynaud’s syndrome is a common and typically benign condition that can significantly impact quality of life, especially in cold climates like Michigan. The foundation of management is protecting your feet from cold exposure, staying active, avoiding known triggers, and keeping your whole body warm. When lifestyle measures aren’t enough, medications like calcium channel blockers can reduce attack frequency by half or more. The most important step is getting properly evaluated to rule out secondary causes — especially if your symptoms started after age 30 or are associated with other health concerns.
Sources
- Herrick AL. “Raynaud’s Phenomenon.” The Lancet, 2012;379(9827):1489-1500.
- Wigley FM, Flavahan NA. “Raynaud’s Phenomenon.” New England Journal of Medicine, 2016;375(6):556-565.
- Pope JE. “The Diagnosis and Treatment of Raynaud’s Phenomenon.” Drugs, 2007;67(4):517-525.
- Hughes M, Herrick AL. “Raynaud’s Phenomenon.” Best Practice & Research Clinical Rheumatology, 2016;30(1):112-132.
Cold, Discolored Toes?
Our podiatrists can determine whether your cold toes are caused by Raynaud’s, poor circulation, peripheral neuropathy, or another condition — and create a management plan to keep your feet safe and comfortable through Michigan winters.
📞 (810) 206-1402 · Howell & Bloomfield Township, Michigan
Do Your Toes Turn White, Red, or Blue in the Cold?
Raynaud’s syndrome causes painful color changes in toes and fingers due to vasospasm. Our podiatrists evaluate and manage circulatory conditions affecting the feet.
Clinical References
- Herrick AL. The pathogenesis, diagnosis and treatment of Raynaud phenomenon. Nat Rev Rheumatol. 2012;8(8):469-479.
- Wigley FM, Flavahan NA. Raynaud’s phenomenon. N Engl J Med. 2016;375(6):556-565.
- Pope JE. Raynaud’s phenomenon (primary). BMJ Clin Evid. 2013;2013:1119.
Insurance Accepted
BCBS · Medicare · Aetna · Cigna · United Healthcare · HAP · Priority Health · Humana · View All →
Howell Office
4330 E Grand River Ave
Howell, MI 48843
Get Directions →
Bloomfield Township Office
43494 Woodward Ave, #208
Bloomfield Township, MI 48302
Get Directions →
Your Board-Certified Podiatrists



Ready to Get Back on Your Feet?
Same-week appointments available at both locations.
Book Your AppointmentPros & Cons of Conservative Care for foot care
Advantages
- ✓ Conservative care first
- ✓ Same-week appointments
- ✓ Multiple insurance accepted
Considerations
- ✗ Self-treatment can mask issues
- ✗ See a podiatrist if pain >2 weeks
Dr. Tom’s Recommended Products for foot care
Affiliate disclosure: As an Amazon Associate, Balance Foot & Ankle earns from qualifying purchases. We only recommend products we use with patients.
Footnanny Heel Cream Dr. Tom’s Pick
Best for: Daily moisturizer for cracked heels
Ready to Get Back on Your Feet?
Same-day appointments in Howell + Bloomfield Township. Most insurance accepted. Dr. Tom Biernacki, DPM & team.
Book Today — Same-Day Appointments Available
Call Now: (810) 206-1402
About Your Care Team at Balance Foot & Ankle
Dr. Tom Biernacki, DPM · Board-Certified Foot & Ankle Surgeon. Specializes in conservative-first care, minimally invasive bunion surgery, and complex reconstruction.
Dr. Carl Jay, DPM · Accepting new patients. Specializes in sports medicine, athletic injuries, and routine podiatric care.
Dr. Daria Gutkin, DPM, AACFAS · Accepting new patients. Specializes in surgical reconstruction and pediatric podiatry.
Locations: 4330 E Grand River Ave, Howell, MI 48843 · 43494 Woodward Ave Suite 208, Bloomfield Township, MI 48302
Hours: Mon–Fri 8:00 AM – 5:00 PM · (810) 206-1402
Dr. Tom’s Raynaud’s Foot Management Protocol
- DASS Medical Compression Socks — Raynaud’s with venous pooling component: graduated compression improves baseline circulation and reduces the venous stasis that makes cold-triggered vasospasm worse.
- Doctor Hoy’s Natural Pain Relief Gel — Raynaud’s episode foot pain and peripheral soreness: arnica + camphor gel applied during the rewarming phase provides topical anti-inflammatory support as circulation returns.
- FLAT SOCKS No-Sock Insoles — Raynaud’s in shoes: FLAT SOCKS moisture-wicking inserts reduce the perspiration that leads to evaporative cooling, a common Raynaud’s trigger inside footwear.
Raynaud’s causing persistent pain, ulcers, or digital loss of sensation? Vascular and rheumatologic evaluation required. Balance Foot & Ankle → (810) 206-1402
Frequently Asked Questions
What causes this condition?
Causes include mechanical stress, biomechanical imbalance, age-related changes, and sometimes systemic disease. Our clinical exam plus imaging identifies the specific driver.
Can it go away on its own?
Mild cases sometimes resolve with rest and supportive footwear. Persistent symptoms past 4-6 weeks rarely resolve without active treatment.
Is surgery required?
Most patients resolve with non-surgical care. Surgery is reserved for refractory cases or structural deformity.

Dr. Tom Biernacki, DPM is a board-certified foot & ankle surgeon (ABFAS & ABPM) at Balance Foot & Ankle Specialists in Southeast Michigan. With over a decade of clinical experience, he specializes in heel pain, bunions, diabetic foot care, sports injuries, and minimally invasive surgery. Dr. Biernacki is a member of the APMA and ACFAS, and his patient education content on MichiganFootDoctors.com and YouTube has made him one of the most-followed foot & ankle educators on YouTube.
More questions patients ask
What is Raynaud's syndrome and why do toes turn white, blue, or red?
Raynaud's syndrome (or phenomenon) is a condition where blood vessels in the extremities — most commonly fingers and toes — undergo exaggerated vasoconstriction (spasm) in response to cold or stress. This causes a characteristic three-phase color change: white (ischemia — blood vessel closure), blue (cyanosis — deoxygenated blood pooling), and red (reactive hyperemia — blood return). The toes and feet become very cold, numb, or painful during attacks. It affects 3–5% of the population. Balance Foot & Ankle in Howell and Bloomfield Township evaluates Raynaud's affecting the feet — call (810) 206-1402.
What is the difference between primary and secondary Raynaud's?
Primary Raynaud's (Raynaud's disease) occurs without an underlying cause — it's a functional disorder of vascular regulation, typically mild, bilateral, and beginning in young women. Secondary Raynaud's (Raynaud's phenomenon) is caused by an underlying condition: most commonly autoimmune diseases (scleroderma, lupus, rheumatoid arthritis), but also thoracic outlet syndrome, medications (beta-blockers, chemotherapy), smoking, and vibrating tool use. Secondary Raynaud's tends to be more severe, can cause tissue ulceration, and requires treatment of the underlying condition. Any new-onset Raynaud's in middle age should be evaluated for secondary causes.
What triggers Raynaud's attacks in the feet?
Common triggers include: cold temperatures (even reaching into a cold refrigerator can trigger attacks), emotional stress and anxiety (stimulates sympathetic nervous system), smoking (nicotine is a powerful vasoconstrictor), caffeine, certain medications (beta-blockers, migraine medications with ergotamine, decongestants, stimulant ADHD medications), and repetitive vibration. Avoiding triggers is the cornerstone of Raynaud's management. Keeping the whole body warm (not just the feet) — since whole-body cooling triggers the reflex — is important. Heated insoles and chemical hand/foot warmers provide targeted warmth during cold exposure.
What treatments are available for Raynaud's affecting the feet?
Conservative measures first: keep whole body warm (layers, especially core), wear thick wool socks and insulated waterproof boots in cold, avoid triggers (cold, stress, smoking, caffeine, vasoconstricting medications). For moderate-to-severe cases: calcium channel blockers (nifedipine 30–60 mg/day — most evidence, reduces attack frequency by 50%), topical nitrates (nitroglycerin paste to toes), phosphodiesterase-5 inhibitors (sildenafil/Cialis — especially for secondary Raynaud's), and IV prostacyclin infusions for severe secondary cases. Omega-3 fatty acids may mildly reduce severity. Balance Foot & Ankle evaluates Raynaud's and coordinates appropriate care.
Can Raynaud's cause permanent damage to the feet and toes?
Primary Raynaud's rarely causes permanent tissue damage — it's uncomfortable but typically benign. Secondary Raynaud's (especially with scleroderma) can cause digital ulcers — painful sores on fingertips and toe tips that are slow to heal and can become infected. Severe, prolonged attacks can theoretically cause tissue death (gangrene), but this is uncommon with proper management. Patients with secondary Raynaud's who develop toe ulcers should see a vascular specialist urgently. Balance Foot & Ankle at 4330 E Grand River, Howell and 43494 Woodward Ave #208, Bloomfield Township evaluates any suspected toe ulcers or non-healing wounds from vascular causes.
Still have a question about coverage or cost? Book online and we will check your benefits before your visit: Book in Howell · Book in Bloomfield Township. Prefer to talk it through first? Call (810) 206-1402.