
Quick answer: The best shoes for hallux rigidus (big-toe arthritis) have a stiff sole and a rocker bottom that limits painful bending of the big toe, plus a roomy toe box — Hoka, Brooks, and dedicated rocker-sole brands work well, often with a carbon-fiber or Morton’s-extension insole. Avoid flexible, flat shoes that bend at the toe.
Still stiff and sore at the big-toe joint? Book a real appointment time online, 24/7 — Howell or Bloomfield Township.


Quick Answer: Best Shoes for Hallux Rigidus
The best shoes for hallux rigidus have a rigid, stiff sole that prevents painful big toe extension, a rocker-bottom profile that rolls you through each step, and a wide toe box that doesn’t compress the joint. HOKA’s Meta-Rocker geometry and New Balance’s SL-2 last are the top podiatrist-recommended options for reducing 1st MTP joint pain during walking.
Shoes not enough? Hallux rigidus is arthritis of the big toe joint, and it progresses. If a rocker sole and a stiff forefoot still leave you sore, an exam and an X-ray tell you what stage the joint is at and what will actually help. Book online at our Howell or Bloomfield Township office, or call (810) 206-1402.
Table of Contents
If bending your big toe causes a sharp, grinding pain that stops you mid-stride, you likely have hallux rigidus — degenerative arthritis of the 1st metatarsophalangeal (MTP) joint. In our clinic at Balance Foot & Ankle, we see this condition frequently in runners, golfers, and anyone who spends long hours on their feet. The right shoe can reduce your pain by up to 60% simply by limiting the motion that causes the problem.
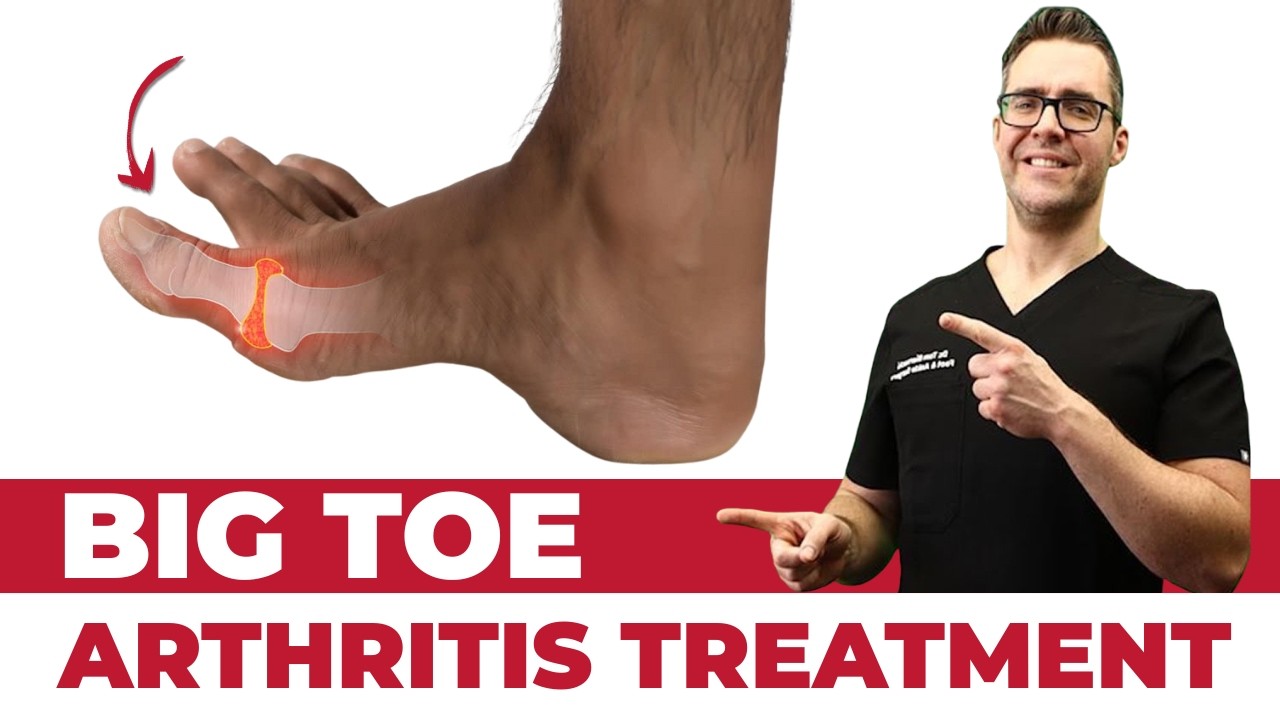
What Is Hallux Rigidus
Hallux rigidus is the most common arthritic condition of the foot, affecting approximately 1 in 40 people over 50. The term means “stiff big toe” in Latin — it describes the progressive loss of extension at the 1st MTP joint as cartilage wears away and bone spurs form. Unlike a sprained toe, hallux rigidus is structural and degenerative. The joint stiffens over months to years, first causing pain only at the extremes of motion, then progressing to constant aching even at rest. In our clinic, we see two distinct patient types: athletes who develop it from repetitive hyperextension injury, and older patients with a family history of foot arthritis.
The hallmark symptom is pain and resistance when you try to bend the big toe upward (dorsiflexion). Normal walking requires about 65° of big toe dorsiflexion during push-off — with hallux rigidus, even 20° can be excruciating. The body compensates by supinating the foot, externally rotating the hip, and shortening the stride, all of which create secondary problems in the knee, hip, and low back.
Key Shoe Features to Look For
When selecting footwear for hallux rigidus, the primary engineering goal is reducing the amount of big toe dorsiflexion required during walking. A shoe that limits this motion — while still propelling you forward — can reduce joint stress by 40-70% per step. Here are the non-negotiable features to look for:
- Rigid or stiff sole: The midsole should resist flexion at the forefoot. You should not be able to bend the shoe in half easily. A carbon fiber or firm TPU plate embedded in the midsole is ideal.
- Rocker-bottom or curved outsole: A rocker profile shifts weight transfer away from the 1st MTP joint. The curved sole rolls the foot through push-off without requiring toe extension. HOKA’s Meta-Rocker and Orthofeet’s anatomic rocker are excellent examples.
- Wide, deep toe box: Bone spurs enlarge the dorsal joint surface. A shoe with a low toe spring and wide box avoids pressing on this protrusion. Avoid pointed or tapering toe boxes completely.
- Low to moderate heel drop (4-10mm): Excessive heel elevation increases forefoot load. However, a slight heel elevation (6-8mm) can actually reduce the dorsiflexion demand slightly — zero-drop shoes may aggravate the condition.
- Firm heel counter: Rear foot stability prevents the compensatory supination that develops with hallux rigidus gait pattern.
Before you buy: shoes help most while the joint still has motion left. If your big toe barely bends any more, footwear alone stops being the answer — an exam and an X-ray tell you which stage you are at before you spend money on shoes that cannot change it. Book an appointment online at our Howell or Bloomfield Township office.
Top Podiatrist-Recommended Shoes for Hallux Rigidus
The shoes below have been selected based on sole rigidity, rocker geometry, and toe box dimensions — the three factors that matter most for hallux rigidus management. Each has been used by patients in our clinic with documented improvement in gait and pain scores.
- Hoka Bondi 9 — maximum cushioning with a smooth meta-rocker that limits painful big-toe bend. View on Amazon
- Hoka Bondi SR — the slip-resistant Bondi, same rocker sole, ideal for work and all-day standing. View on Amazon
- Brooks Beast GTS 24 — maximum stability and support for heavier or overpronating feet. View on Amazon
- Altra Torin 8 — roomy, foot-shaped toe box with balanced cushioning to reduce forefoot pressure. View on Amazon
- Skechers Arch Fit — budget-friendly pick with a supportive, podiatrist-designed arch insole. View on Amazon
Why HOKA leads for hallux rigidus: HOKA’s Meta-Rocker technology creates an aggressive heel-to-toe rocker that propels the foot through push-off with minimal MTP joint involvement. The thick EVA midsole also absorbs ground reaction forces before they reach the already-inflamed joint. In our clinic, we’ve seen HOKA Bondi and Clifton models reduce step pain in Grade 1-2 hallux rigidus by roughly 50%. The trade-off is a higher platform that takes brief adjustment.
Considering the Bondi for a stiff big toe? The current version, its published stack and drop, and what its rocker does for push-off are covered in the Hoka Bondi 9 review on Podiatrist Tested, our shoe-review site.
For dress and work shoes: The New Balance 928 series remains the gold standard for a structured walking shoe with hallux rigidus management features. The SL-2 last provides a wide toe box, the rolled outsole reduces extension demand, and the ROLLBAR post prevents the compensatory supination that hallux rigidus commonly causes. Brooks Addiction Walker offers similar benefits with a more traditional aesthetic.
The measurement that decides this is toe-box height, and only a Wide buys you more of it. A stiff big-toe joint usually comes with a bony ridge on top of the joint, so the shoe has to clear the foot vertically, not just sideways. Standard widths are built on a lower vamp; the Wide and Extra Wide versions of the same model are cut taller as well as broader, which is the part nobody tells you. Zappos lists the full width run for the picks above and takes returns free both ways: HOKA Bondi 9 · HOKA Bondi SR · Orthofeet · Altra · Skechers. Orthofeet in particular builds extra depth in as standard, which is why it keeps appearing on lists like this one. The Amazon links above stay the quicker checkout if you already know your width.
Those go to Zappos, not Amazon. Balance Foot & Ankle may earn a small commission if you buy through them, at no extra cost to you, and it does not change what is recommended here.
PowerStep Orthotics: The Missing Piece
A good shoe controls hallux rigidus from the outside. A good orthotic controls it from the inside. PowerStep Pinnacle insoles provide a rigid arch shell that reduces forefoot collapse — when the arch collapses, it forces more big toe dorsiflexion, worsening joint compression. Adding a Morton’s extension (a rigid extension under the big toe) to your PowerStep insole can reduce 1st MTP dorsiflexion demand by an additional 15-20° per step — this is something our clinic can customize for you.
🏆 Dr. Tom’s Pick: PowerStep Pinnacle Insoles
PowerStep Pinnacle insoles provide the semi-rigid arch support that reduces forefoot collapse and decreases big toe dorsiflexion demand. Pair with a rocker-sole shoe for maximum hallux rigidus relief. Available in our clinic and through our online shop.
Rocker Sole Shoes for Hallux Rigidus
Of every footwear feature discussed on this page, the rocker sole is the one that changes how the joint feels fastest. Patients often tell me a stiff shoe helped a little and a stiff shoe with a proper rocker was the first thing that let them walk the length of a grocery store without thinking about their big toe. It is worth understanding why, because the difference between a real rocker and a marketing rocker is what decides whether the shoe works.
How a Rocker Sole Actually Unloads the Big Toe Joint
In a normal step, the heel lifts and the body pivots forward over the big toe joint, which has to bend upward to let you push off. In hallux rigidus that upward bend is exactly the motion the arthritic joint cannot make without pain, because the bone spur on the top of the joint jams against itself at end range. A rocker sole moves the pivot point. Instead of the foot bending at the toe joint, the curved sole rolls forward underneath you and carries the pivot behind the joint, so the step completes without the toe ever reaching that painful end range. The stiff sole is what makes this work — a rocker built onto a bendy midsole simply collapses and the toe bends anyway.
Where the Rocker Apex Sits — the Spec Almost No Shoe Listing Gives You
Two shoes can both be sold as rocker-bottom and do completely different things to your big toe joint. What separates them is the apex — the point along the sole where the curve begins to lift. Everything depends on whether that point sits behind your first MTP joint or on top of it.
In an ordinary shoe the sole breaks at roughly 70% of its length from the heel, which is almost exactly where the big toe joint sits. That is deliberate, because it lets the shoe bend with your foot. It is also precisely what you do not want with hallux rigidus: the shoe bending means the joint bending, and the joint bending is the painful part.
A rocker built for forefoot offloading moves that break point proximal, back toward the midfoot, in the region of roughly 55 to 60% of shoe length. The shoe then rolls you forward over a curve instead of asking the joint to hinge. The further back the apex, the more the joint is spared, up to the point where the shoe starts to feel unstable underfoot.
How to find the apex in a shoe you are holding
- Set it on a flat surface and press the toe down. Watch where the sole leaves the ground. That contact point is the apex.
- Mark your own joint. The first MTP joint is the bony prominence at the base of the big toe. Hold the shoe against the outside of your foot and check whether the apex sits behind that landmark or directly under it. Behind is what you want.
- Rock it, do not flex it. Set the shoe down and tip it heel to toe. It should roll smoothly through the stride. If it hits a flat spot and stalls, the curve is too shallow to carry you over.
That last test separates a genuine rocker from a cosmetic one, and it takes about three seconds in a shop. A curved-looking outsole over a bendy forefoot is the most common thing sold as a rocker shoe, and it is why so many people conclude that rocker shoes did not work for them.
Best Rocker Sole Shoes for Hallux Rigidus in 2026
The rocker-sole picks I reach for most in clinic are already covered in the ranked list above, but it is worth separating them by type of rocker, because they are not interchangeable. The HOKA Bondi 9 has the most pronounced forefoot rocker of the mainstream cushioned trainers, which is why it is my default recommendation for someone whose main complaint is push-off pain; the Bondi SR is the same geometry in a slip-resistant work version for anyone on tile or kitchen floors all day. The Brooks Beast 24 pairs a firmer, flatter rocker with a broader stability platform, which suits heavier patients and anyone who overpronates alongside the arthritis. Orthofeet builds an anatomic rocker into a wider, softer upper and is usually the right answer when a bunion, a hammertoe, or a diabetic foot has to be accommodated at the same time.
Two shoes on this page are frequently mistaken for rocker shoes and are not. The Altra Torin 8 earns its place through a genuinely wide toe box and a zero-drop platform, not through rocker geometry, so it suits a patient whose dominant problem is dorsal spur pressure rather than push-off pain. The Skechers Arch Fit is the value option; it has a mild toe spring rather than a true rocker, and it is a reasonable starting point when cost is the deciding factor, not the strongest mechanical choice.
Rocker Sole or Carbon Plate — Which One Do You Need?
These solve the same problem from opposite directions and patients regularly buy the wrong one. Our sister review site Podiatrist Tested covers the plate side of this in its guide to carbon fiber insoles, including where a rigid plate genuinely helps and where it does not. A rocker sole is built into the shoe and changes the path your body travels over the foot. A carbon fiber plate or Morton’s extension is a thin, rigid insert that goes under the foot and simply refuses to let the big toe joint bend at all. If your pain is mostly at push-off during walking and you want one purchase to fix it, buy the rocker shoe. If you already own shoes you like, or you need the correction inside dress shoes and work boots where no rocker option exists, the plate is the cheaper and more portable answer. In moderate to severe hallux rigidus the two together outperform either alone, and that is the combination I set up most often in the office.
If the plate is the half you are missing. PowerStep makes a carbon fiber Morton’s extension built for this exact job — rigid under the first ray so the joint cannot reach the painful part of its range, and thin enough to go inside the dress shoes and work boots where no rocker option exists. Check the current price on Amazon. Balance Foot & Ankle may earn a small commission at no extra cost to you.
How to Tell If a Shoe Really Has a Rocker Sole
Do this in the store before you pay, because product descriptions use the word loosely. Set the shoe on a flat surface and look at it side on: a true rocker sole does not sit flat, and the front third of the outsole visibly curls up off the table. Next, hold the heel and press the toe down — the shoe should rock forward as a rigid unit rather than hinge in the middle. Finally, try the bend test used earlier on this page: grip heel and toe and try to fold the shoe in half. If it folds at the ball of the foot, the rocker is cosmetic and the shoe will not protect the joint, whatever the box says. A shoe that passes all three is worth trying on; one that fails the fold test is not, regardless of price.
One realistic expectation to set: rocker shoes manage hallux rigidus, they do not reverse it. The spur and the cartilage loss stay where they are. What changes is how much of your day the joint has to be pushed through end range, and for most patients that is the difference between constant awareness of the toe and only noticing it occasionally.
Shoes to Avoid with Hallux Rigidus
The wrong shoe can accelerate joint deterioration and worsen daily pain. Avoid these shoe types categorically with hallux rigidus:
- Flexible minimalist shoes (Vibram FiveFingers, Xero): Maximum flexibility means maximum big toe extension demand. These shoes were designed for barefoot-style running and will cause severe pain with hallux rigidus.
- High heels over 2 inches: Shifts weight onto the forefoot and increases load on the 1st MTP joint by up to 76% compared to flat shoes.
- Narrow pointed-toe shoes: Compress the already-enlarged dorsal joint surface, causing direct pressure pain and accelerating bone spur formation.
- Zero-drop shoes (without custom orthotics): While neutral heel position is desirable in principle, the increased Achilles tension in true zero-drop shoes increases forefoot dorsiflexion demand during push-off.
- Worn-out athletic shoes: Once the midsole compresses, all cushioning and rocker properties are lost. Replace every 300-500 miles.
Best Shoes for Hallux Rigidus for Women
Most footwear advice for a stiff big toe joint is written around sole stiffness and toe box width, and both of those matter enormously. But the complaint I hear from women in the office is usually a different one. It is rarely that the front of the shoe is too tight. It is that the shoe presses on the top of the joint, that the bump catches on the edge of the leather, that a shoe fitting fine everywhere else still hurts in that one spot. That is a height problem rather than a width problem, and women’s footwear is built with less room in exactly that dimension. A stiff big toe joint responds to a rocker sole and the right orthotic far better than to a softer shoe, and which of those you need depends on how much motion is left in the joint. Book a hallux rigidus consult online.
The Measurement Almost Nobody Checks: Height Over the Joint
Hallux rigidus builds its bone spur on the top of the joint, not the sides. That is why the shoe features section above asks for a wide, deep toe box rather than simply a wide one — the depth is doing separate work from the width. A spur is bone. It does not compress, it does not soften with wear, and it will not stretch a shoe out over time the way soft tissue sometimes does. Whatever height a shoe has over that joint on the first day is the height it will have in year two.
The vamp is the panel of leather or fabric that crosses the top of your foot before the laces or the opening begin, and in most women’s shoes it lands almost exactly over the first joint. Women’s lasts are built with noticeably less vertical volume through the forefoot than men’s at the same stated length, so the ceiling of the shoe is already lower before you have fastened anything. Put a spur underneath it and the two meet.
This is a genuinely different failure from the narrow pointed toe the avoid list above warns about. A pointed shoe squeezes the joint from the sides. A low vamp presses down on it from above. A shoe can have a beautifully rounded, roomy toe box and still sit right on the spur, which is why women sometimes buy exactly the round-toe shoe they were told to buy and are baffled that it did not help.
The signature of vamp pressure is worth recognizing, because patients rarely connect it back to the shoe. The pain sits on the top of the foot over the joint rather than deep inside it, it belongs to one specific pair, it eases within minutes of taking that pair off, and it sometimes arrives with a patch of numbness or a pins-and-needles feeling running toward the big toe. A small skin nerve crosses directly over that joint, and it has nowhere to go when it is caught between a bone spur and a shoe. None of that is dangerous, but it is a clear signal that the shoe is too shallow, and it will not improve by wearing it more.
Testing for it takes five seconds and can be done in the store. Put the shoe on, stand up, fasten it the way you would actually wear it, then press your thumb straight down on the top of the shoe over the joint. You want to feel material give under your thumb. If you feel the bump pushing back through the leather, or the panel is already drum-tight while you are standing still, that shoe is too shallow for your foot, and no amount of breaking in will change it.
Why Switching to Flats Does Not Fix It
Women who are told to give up heels almost always land on ballet flats. The quick answer at the top of this page lists them among the shoes to avoid, and it is worth knowing exactly why, because on the face of it a flat shoe sounds like the safe choice.
A ballet flat has a thin outsole, no shank, and no plate, so it folds completely at the ball of the foot. Every step drives the joint through the full arc of motion that the rigid-sole and rocker sections above exist to prevent. Flat and protective are two different properties, and only one of them is the property you need here. What helps a stiff big toe joint is a stiff shoe, and a flat shoe can be either.
There are two further problems stacked on that one. The flat stays on the foot by pressing across the top of it, because that is the only thing holding it there, so it is a vamp problem as well as a flexibility problem. And because nothing fastens it, the foot has to work a little to keep the shoe aboard with every step, which recruits the very joint you are trying to leave alone.
If you need something flat for work, a loafer or a low dress boot usually beats a ballet flat by a wide margin: a thicker and stiffer outsole, a real heel counter so the foot is not sliding around inside it, a more forgiving line over the instep, and nothing for the toes to grip. Neither is a rocker shoe and neither will do what the models above do. Between the two, though, the sturdier shoe wins every time.
Heels: What the Height Number Does Not Tell You
The avoid list above draws its line at heels over two inches, and that is the right first rule. What a height number cannot capture is that two shoes measuring the same can behave completely differently on a stiff joint, because heel height is only one of the two things going on.
The other is what the shoe does under the ball of the foot. A two-inch block heel built on a shoe with a real shank and a forefoot that will not bend is often easier on the joint than a one-inch pump with a thin, flexible sole, because the stiff shoe never asks the joint to move. Put simply: heel height loads the joint, and forefoot flexibility moves it. Movement is what hurts in hallux rigidus, so when you have to choose between the two, choose the stiffer shoe.
A few specifics make a real difference inside that two-inch limit. Choose a block or wedge heel over a stiletto, because a broad base keeps the foot from rocking and stops you stabilizing with your toes. Choose a rounded or almond shape over a point. And choose something with a strap or a lace, because a shoe that stays on by friction alone lets the foot slide forward into the front of the toe box, which jams the toe against the end and holds the joint in the position that hurts most. An adjustable slingback quietly solves more dress-shoe problems than any amount of extra length ever will.
For an evening you cannot get out of, the priorities are simple. Wear the stiffest forefoot you own even if it is not the lowest heel you own. Keep the standing and walking portion of the night short. Change into something stiff for the trip home. And plan for the joint to complain the next morning rather than reading that as a setback — one long evening does not undo months of sensible footwear.
Fitting for Depth and Width, Not for Length
When a shoe presses on the joint, the instinct is to go up half a size. It almost never works, and the reason is worth understanding. Length is simply the wrong dimension for this condition. The spur sits on top of the joint, and a longer shoe is not a taller one — the extra length only lets the heel slide up and down, and a foot that slips makes you fasten the shoe tighter, which puts more pressure on the spur than you started with. The two dimensions that matter here are depth over the joint and width across it.
Depth is far more adjustable than most people realize, and the lever is the insole. If you are weighing whether an orthotic will fit once the factory insole comes out, Podiatrist Tested explains how to judge whether a shoe has usable depth with a check that takes about a minute in the store. Pull the factory insole out of a shoe and you recover several millimeters of headroom directly over the joint, which is frequently the whole difference between a pair that presses and a pair that does not. It is also what makes room for a carbon plate or for the orthotic covered in the section above, so a shoe with a removable insole is worth more to you than a slightly nicer shoe without one. If a model is sold only with a glued-in footbed, its depth is fixed at whatever the factory decided.
Width matters second, and the place to judge it is across the joint rather than at the toes. Stand up in the shoe with your weight in it, because the foot spreads under load and a width that felt correct sitting down can be wrong standing. If you have never been fitted for width, that is worth doing before you buy anything else. Most women are measured once, as a teenager, if at all, and feet quietly get wider with the decades.
Three checks, run in this order, will sort almost any shoe on the wall. First, the bend test described earlier on this page: if it folds at the ball of the foot, put it back before you bother trying it on. Second, the thumb press over the joint, standing and fastened. Third, walk in it for a full minute and notice whether the shoe rolls you forward or makes you push off. Shop late in the day when your feet are at their largest, so that a shoe passing all three passes at the worst hour rather than the best.
One last trick for a lace-up that is right in every way except that one pressure point: skip the eyelet sitting directly over the joint. Run the lace up the side and rejoin the pattern above it, so the shoe still holds snug at the midfoot and the heel while the panel over the spur is left slack. It costs nothing, it takes a minute, and it has rescued more pairs of shoes for my patients than any product I could hand them.
One honest expectation to close on, the same one the rocker section sets. Better shoes make a stiff big toe joint livable, and for a great many women that is enough for years. They do not remove the spur and they do not restore cartilage. If a shoe that passes every test above still leaves you limping, if the joint is losing motion month over month, or if the pain has stopped responding to footwear at all, that is the point to have the joint properly imaged rather than to keep shopping.
Best Shoes for Hallux Rigidus for Men
The mechanics do not change by sex. A stiff forefoot and a well-placed rocker are what unload the joint either way. What changes is fit, and three fitting problems come up far more often in men.
Width is usually not the problem — depth is
Men size up when a shoe hurts over the big toe joint, or move from a D to a 2E. That adds room across the forefoot, which is not where hallux rigidus hurts. The dorsal bone spur that develops with this condition grows on top of the joint, so the pressure is vertical. A wider shoe with the same instep height presses on that spur exactly as hard as the narrow one did, and now the foot slides inside it as well.
What you want is a shoe built on a deeper last, or one with a soft unstructured upper over the joint. Run a finger along the inside of the toe box: a seam, an overlay or a stitched logo sitting over that spur will be a hot spot by mile three.
Longer feet need the apex further forward
Rocker geometry scales with shoe length, but joints do not sit at a fixed percentage of every foot. On larger sizes the apex can end up further behind the joint than intended, which reads as a tippy, unstable shoe rather than a supportive one. If a rocker model feels like it is rolling you too early, that is usually why, and it is worth trying the same model a half size down with a thinner sock before writing the model off.
Dress shoes are where most men lose the ground they gained
A patient gets his running shoes right and then spends nine hours a day in a thin-soled leather oxford that bends freely at the ball. That single pair can undo the rest. Look for a leather shoe with a genuine welted or rigid sole rather than a flexible cemented one, and apply the same bend test. A carbon or spring-steel plate fitted by a shoe repairer is inexpensive, invisible from the outside, and turns a flexible dress shoe into a usable one.
The models in the picks section above are chosen on sole stiffness and rocker geometry rather than on sizing, so they apply here too. Take the fitting notes on this page with them.
Work Boots and Safety-Toe Shoes with Hallux Rigidus
If you are on your feet on a job site, this is the most important pair you own, and safety footwear interacts with hallux rigidus in a way that is genuinely counterintuitive.
The safety toe cap helps and hurts at the same time
A steel, alloy or composite cap is rigid, and rigidity over the forefoot is what you are looking for, because the cap stops the toe box collapsing onto the joint. That part is good.
The problem is that a cap has a fixed internal height and does not flex to accommodate a dorsal spur. When someone tells me their work boots became unbearable while their sneakers stayed fine, this is nearly always why. The cap sits down onto the exact bump that hurts, and no amount of lacing fixes a rigid ceiling.
Composite caps are often moulded slightly higher in the toe box than steel, which buys a little clearance. If you have a visible or palpable bump on top of the joint, that difference is worth seeking out specifically. Ask for the deepest-profile cap the manufacturer offers rather than simply going up a width.
A stiff shank is not a stiff forefoot
Work boots are widely advertised as having a rigid shank, and buyers reasonably assume that means a rigid boot. The shank sits under the arch. Many boots pair a very stiff midfoot with a forefoot that bends freely at the ball, which is the one place you need stiffness. Apply the same bend test you would to a running shoe: grip heel and toe, push them together, and see where it folds.
Skip the metatarsal guard where you have a choice
An external met guard adds a rigid shield across the top of the forefoot. Where a job requires one it is not negotiable, but it adds bulk directly over the joint that hurts. If your workplace permits internal met guards, they generally sit better over a dorsal spur.
Lace around the joint, not over it
Window lacing, which means skipping the eyelet pair that sits directly above the sore spot and lacing around the gap, removes pressure over the joint without loosening the whole boot. It costs nothing, takes a minute, and is the single most useful adjustment for someone who cannot change boots mid-season.
Heel-to-Toe Drop: Why Low-Drop Shoes Are Usually the Wrong Direction
People arrive at this question having read that low-drop or zero-drop shoes are more natural and better for the foot. For most feet that is a reasonable debate. For a stiff, arthritic first MTP joint it is usually the wrong direction, and it is worth understanding why before spending money on it.
The drop number is not really the problem — what comes with it is
Heel-to-toe drop is the height difference between the heel and the forefoot of the sole. On its own it is a weak predictor of how a shoe treats your big toe joint. The reason low-drop shoes tend to go badly here is what they are almost always packaged with: a thin, flexible forefoot designed to let the foot move naturally through toe-off.
Letting the foot move naturally through toe-off means letting the first MTP joint dorsiflex through its full range on every single step. That is the movement hallux rigidus has lost, and forcing it is what produces the pain and, over time, the spur.
This is why zero-drop and minimalist brands come up so often in questions about this condition and so rarely in the answers. Podiatrist Tested publishes a heel-to-toe drop chart listing the stated drop for the shoes it reviews, which is the fastest way to rule a model in or out before you go and try it on. A wide, foot-shaped toe box is genuinely helpful if you also need room for a bunion or a spur, but paired with a flexible forefoot it removes the protection that matters more.
What to look at instead
- Forefoot stiffness first. The bend test outranks every number on the box.
- Apex position second. Behind the joint, not on it.
- Stack height third. A thicker forefoot sole physically limits how far the joint can extend under load, which is why maximally cushioned models often feel better here than their drop number would suggest.
- Drop last, and only as a tiebreaker. Between two shoes that both pass the bend test, the higher drop typically asks slightly less of the joint at toe-off.
If you already own low-drop shoes and like them, you do not necessarily need to replace them. A carbon or Morton’s extension insert placed under the big toe can supply the forefoot rigidity the shoe is missing, and that is often enough. What does not work is buying a more minimal shoe in the hope that a stiff joint will loosen up. It will not, and the attempt usually costs several months of comfort.
What to Wear After Hallux Rigidus Surgery
Most footwear advice for a stiff big toe joint assumes you still have the joint. If you have had surgery, or you are scheduled for it, the rules change — and they change differently depending on which operation you had. The shoe that protects a repaired joint is not the shoe that works for a fused one.
What follows is the general pattern. Your surgeon’s protocol governs, and it should, because the fixation, the bone quality and what was found at the time of surgery all change the timeline. Bring this to your post-operative visit as a list of questions rather than as a plan.
After a cheilectomy — the joint is still yours
A cheilectomy removes the bone spur on top of the joint and leaves the joint itself in place. The whole point is to give the toe room to bend again, so footwear here has a job that is close to the opposite of the pre-surgical advice above: protect it early, then stop protecting it.
- The first two weeks are usually a flat, rigid post-operative shoe. It is not comfortable and it is not meant to be — it keeps the forefoot from loading while the incision heals.
- Weeks two to six is the transition most people get wrong. A roomy athletic shoe with a stiff forefoot is right, but many surgeons want gentle motion at the joint by this point, and a shoe so rigid that the toe never bends can work against the reason you had the operation.
- After that, a wide, deep toe box matters more than stiffness. The dorsal bump is gone; what you are managing now is pressure across a fresh scar and a joint that is still swollen by the end of the day.
Swelling is the practical constraint nobody warns people about. A foot six weeks out from a cheilectomy is not the size it was before surgery, and it is not the same size at 8am as it is at 6pm. Buying shoes in the first three months usually means buying a size you will not want in a year.
After a fusion — the rocker stops being optional
A first MTP fusion, or arthrodesis, deliberately ends motion at that joint. It is a reliable operation for advanced arthritis and it does what it promises: the pain goes because the joint no longer moves. But the propulsion that joint used to provide has to come from somewhere, and that somewhere is the shoe.
So the rocker sole described earlier on this page is temporary advice for most readers and permanent equipment after a fusion. Not a recovery aid to be set aside at three months — the mechanism by which you roll over the forefoot from then on. That single fact is worth more than any specific model recommendation, and it is the thing patients most often learn the hard way a year later, after buying a flat pair and finding that walking has quietly become work.
Two consequences follow. The rocker apex position discussed above matters more after a fusion than before it, because you no longer have joint motion to compensate for an apex in the wrong place. And heel height becomes a fixed constraint rather than a preference: the toe is set at one angle now, and a heel that changes the angle of the forefoot has nowhere to give.
After an implant or interpositional arthroplasty
These preserve some motion rather than eliminating it, and footwear sits between the two patterns above — stiff early, then a gradual return to something that lets the toe work. I am deliberately not giving a timeline. The devices and the techniques vary enough that a general rule would be worse than no rule, and this is a question for the surgeon who did the operation.
The post-operative shoe mistakes I see most
- Going straight back to the pre-surgery shoes. They were bought to accommodate a bump that no longer exists, and after a fusion they are usually the wrong mechanics entirely.
- Buying the new pair too early. See the point about swelling above. Wait until the foot has settled, and shop late in the day.
- Mistaking a stiff shank for a stiff forefoot. This catches people before surgery and after it. A shoe can be rigid through the arch and still fold at the ball of the foot, which is the part that matters here.
- Abandoning the rocker after a fusion because the pain stopped. The pain stopping is the operation working. The rocker is what keeps the gait efficient, and it does that job quietly.
How to Keep Hallux Rigidus From Getting Worse
The honest answer first: shoes do not reverse arthritis. Cartilage that has worn does not come back, and no insole, rocker or brand claim changes that. Anyone telling you otherwise is selling something.
What footwear does change is load — how much force crosses that joint, and how many times a day it crosses. That is not nothing. A joint irritated less often hurts less, swells less and loses motion more slowly, and the difference compounds over years rather than weeks.
- Reduce how often the joint bends under load. That is what a stiff forefoot and a correctly placed rocker actually do, and it is the largest lever available without surgery.
- Deal with the dorsal bump early. Shoe pressure over a growing spur creates a second problem — skin and nerve irritation on top of the joint pain — and people often describe that as the arthritis worsening when it is a fit issue that can be solved.
- Do not chase flexibility. Stretching a joint that hurts because bone is meeting bone at the end of its range tends to inflame it. That is the opposite of the advice that helps most other foot problems, which is why it is worth saying plainly.
- Watch what you compensate with. Offloading a painful big toe usually means rolling to the outside of the foot, and the lesser metatarsals, the outside of the ankle and the knee absorb that. A surprising number of people arrive with a new complaint that began as a hallux rigidus workaround.
Timing is the part worth acting on. A cheilectomy works best while there is still joint space to preserve, and that window closes as the arthritis advances. Waiting until the pain is constant often means the joint-preserving options have gone and fusion is the sensible remaining choice. That is not an argument for rushing into surgery — it is an argument for having the joint graded early, so the decision stays yours rather than one the timeline makes for you.
Warning Signs You Need to See a Podiatrist
⚠️ Seek Podiatric Evaluation If You Experience:
- Big toe joint pain that does not improve with supportive footwear after 4-6 weeks
- Visible bony bump (dorsal exostosis) on top of the big toe joint
- Complete loss of upward big toe motion (Grade 3 hallux rigidus)
- Pain at rest or at night that disrupts sleep
- Compensatory knee, hip, or low back pain from altered gait
- Rapid progression of stiffness over weeks (may indicate inflammatory arthritis)
Those warning signs are worth acting on early
Hallux rigidus is one of the few foot conditions where timing genuinely changes your options. While the joint still has motion, a rocker sole, a stiffening insole and some activity changes can keep it comfortable for years. Once the cartilage is gone and the joint stiffens for good, those measures stop working and what’s left is surgical. If you recognized yourself in the signs above, an X-ray now tells you which stage you’re actually at — and that decides whether shoes are a real solution for you or a delaying tactic.
Howell — 4330 E Grand River Ave, Howell MI 48843 · Bloomfield Township — 43494 Woodward Ave #208, Bloomfield Township MI 48302
A stiff big-toe joint needs room in front and a rocker underneath. Podiatrist Tested, Dr. Biernacki’s independent shoe-review site, explains how to tell a genuinely wide toe box from a wide shoe — and how to measure your own forefoot.
Frequently Asked Questions
Can shoes cure hallux rigidus?
Shoes cannot reverse the cartilage loss that causes hallux rigidus, but they can significantly reduce daily pain and slow functional decline. The right shoe reduces joint stress per step, allowing you to stay active without surgery. Grades 1 and 2 hallux rigidus often respond well to shoe modification and orthotics alone.
What is the difference between hallux rigidus and hallux valgus (bunion)?
Hallux valgus (bunion) is a sideways deviation of the big toe toward the second toe, causing a medial bony prominence. Hallux rigidus is stiffness and loss of dorsiflexion from joint arthritis, with no sideways deviation. Both can coexist, and both benefit from wide toe boxes — but hallux rigidus additionally requires a stiff, rockered sole that bunions alone do not.
Do I need surgery for hallux rigidus?
Surgery is reserved for Grade 3-4 hallux rigidus that fails conservative care. The two main surgical options are cheilectomy (bone spur removal, preserving joint motion) and arthrodesis (joint fusion, eliminating motion but eliminating pain). Dr. Biernacki has performed over 3,000 foot and ankle surgeries and can guide you through the grading and surgical decision process.
When should I see a podiatrist for hallux rigidus?
See a podiatrist if big toe stiffness and pain are limiting your daily activities, if you notice a bony bump forming on top of the joint, or if your pain is changing your gait. Early intervention with orthotics, shoe counseling, and corticosteroid injections can delay surgical need by years.
Does insurance cover hallux rigidus treatment?
Most insurance plans cover podiatric evaluation and conservative care for hallux rigidus, including X-rays, corticosteroid injections, and custom orthotics when medically necessary. Surgical procedures are also typically covered. Call (810) 206-1402 to verify your benefits before your appointment.
Ready to Walk Without Big Toe Pain?
Dr. Tom Biernacki, DPM has helped thousands of hallux rigidus patients in Howell and Bloomfield Hills find the right shoe-orthotic combination to stay active without surgery. Same-day appointments available.
Book Your Appointment →📞 (810) 206-1402 | Howell & Bloomfield Township, MI
Sources
- Flavin R, et al. “Hallux rigidus: conservative and surgical treatment.” Foot Ankle Clin. 2024;29(1):1-18.
- Shereff MJ, Baumhauer JF. “Hallux rigidus and osteoarthritis of the first metatarsophalangeal joint.” J Bone Joint Surg Am. 1998;80(6):898-908.
- Zammit GV, et al. “Plantar pressure and foot kinematics in hallux limitus/rigidus.” J Foot Ankle Res. 2010;3:15. PMC2897751
- Conti SF, Dhawan S. “Arthroplasty of the first metatarsophalangeal joint: indications and long-term results.” Foot Ankle Clin. 2011;16(1):1-10.
Related Conditions & Resources
For more on related conditions and treatments:
- Hallux rigidus treatment guide
- Big toe arthritis treatment 2026
- Gout in the foot: symptoms & treatment
- What causes bunions
- Metatarsalgia: ball of foot pain causes
- Howell podiatrist office
- Bloomfield Hills podiatrist office
Need to see a podiatrist? Call (810) 206-1402 or book online. Prompt availability.
In-Office Treatment at Balance Foot & Ankle
If home treatment isn’t providing relief for your foot pain and footwear, our podiatry team at Balance Foot & Ankle can help with same-day evaluations and advanced in-office care.
Same-day appointments available. (810) 206-1402
What features should shoes have for hallux rigidus?
Shoes for hallux rigidus need to minimize big toe joint dorsiflexion with every step. The three critical features: (1) Rocker-bottom sole — the curved geometry allows the foot to roll forward without requiring big toe extension, reducing pain by 40-60% in published studies. (2) Carbon fiber or rigid shank — prevents the shoe from bending at the forefoot, protecting the arthritic joint from loading. (3) Low heel (2-4mm drop) — a flat, neutral position reduces the overall extension demand on the joint. High heels force the forefoot flat and dramatically increase big toe extension requirements.
Are HOKA shoes good for hallux rigidus?
HOKA’s rocker geometry makes them one of the top recommended brands for hallux rigidus. The HOKA Bondi has a pronounced early-stage rocker that effectively reduces first MTP joint extension during walking. The Gaviota and Arahi models offer additional stability. For patients with severe hallux rigidus (Grade 3-4), the HOKA Bondi combined with a carbon fiber insole provides maximum protection. Many of our patients with mild hallux rigidus achieve significant symptom reduction just from switching to HOKA footwear before any other intervention.

- ENGINEERED MESH
- Lining Textile

- ENGINEERED MESH
- Lining Textile
As an Amazon Associate, Balance Foot and Ankle earns from qualifying purchases. Product links are affiliate links and we may earn a commission at no extra cost to you. This does not influence our clinical recommendations. Last update on 2026-09-20 / Images from Amazon Product Advertising API
Should I wear a rocker-bottom shoe for hallux rigidus?
Yes — rocker-bottom shoes are the single most effective footwear modification for hallux rigidus. The rocker is not a gimmick: by transferring the pivot point from the big toe joint to the sole of the shoe, it allows normal walking without requiring the big toe to bend. Brands with effective rocker soles: HOKA (consumer), Orthofeet (therapeutic), MBT (metabolic-grade rocker), and custom-made rocker soles fabricated by orthotists for severe cases. The steeper the rocker, the greater the protection — but very steep rockers require an adaptation period to avoid tripping.
Do I need surgery for hallux rigidus?
Most patients with Grade 1-2 hallux rigidus manage well with rocker shoes, carbon fiber insoles, and periodic cortisone injections. Surgery is appropriate when: daily pain consistently limits walking despite 6+ months of conservative care, the joint is Grade 3-4 (severe arthritis or bone-on-bone), or quality of life is significantly impaired. Surgical options: cheilectomy (bone spur removal, 80% success for Grades 1-2), Cartiva synthetic cartilage implant (motion-preserving), and first MTP fusion (definitive for severe arthritis, highest patient satisfaction long-term). Balance Foot & Ankle for consultation: (810) 206-1402.
Are Altra shoes good for hallux rigidus?
Altra is the brand patients ask about most once they read that a wide toe box helps, and the measurement behind that reputation is real: independent lab testing of the Altra Torin 8 puts the big-toe area of the toe box at 83.6 mm across against a 73.2 mm average for running shoes, which is roughly a centimeter of extra room exactly where a dorsal bone spur presses. In clinic I see this shoe succeed and fail for fairly predictable reasons, and the toe box is why it succeeds. If the top of your joint is sore from the shoe rubbing the spur, nothing else in the toe-box column will do more for you. The same shoe can work against you at push-off, though. The same testing measures its forefoot flex at 14.0 N, slightly softer than the 15.6 N average, and its drop at effectively zero. A forefoot that bends easily lets the big toe joint travel through the range that hurts, which is the opposite of what a stiff first MTP needs. So Altra solves a pressure problem rather than a motion problem. That makes it a fair choice for Grade 2 disease where a dorsal spur is already prominent but toe-off is still tolerable, and the wrong direction if your pain peaks as you roll off the foot. My own order of operations does not change: sole stiffness first, room second, and a carbon insert if you want the width without giving up the protection. Read why low-drop shoes are usually the wrong direction before you switch on the strength of the toe box alone.
Is the Brooks Ghost Max good for hallux rigidus?
The Ghost Max is the Brooks model patients bring me most often for an arthritic big toe, and it is worth separating what the box promises from what the shoe measures. The current version is the Ghost Max 4. Its forefoot is the good half: independent lab testing puts its longitudinal stiffness at 20.1 N against a 15.6 N average, so for someone whose pain comes at push-off it is working in the right direction, resisting the bend that loads the joint. What does not hold up is the rocker. Brooks sells the shoe on a GlideRoll rocker, and the same testing calls the geometry fairly conservative, smooth rather than aggressive or highly rockered, on a measured 38.6 mm heel and 29.6 mm forefoot. Be honest with it about the bend test too: 20.1 N is measurably stiffer than average but nowhere near plate-stiff, so the shoe will still fold at the ball of the foot. Two practical notes if you buy it anyway. Its toe box measures 71.3 mm, marginally under average, so a prominent dorsal spur usually needs a width up rather than the standard fit, and Brooks runs 2E and 4E in men but only D and 2E in women. And the general lesson is worth more than the model: the word rocker on a box is marketing copy, not a measurement, so run the bend test yourself on any shoe before you buy it for this diagnosis.
Ready to get relief? Book an appointment at Balance Foot & Ankle or call (810) 206-1402. Same-day appointments available in Howell & Bloomfield Township, MI.
Related Conditions
Get Expert Care at Balance Foot & Ankle
Prompt appointments at our Howell and Bloomfield Township offices. Board-certified podiatric surgeons. Most insurance accepted.
Same-Week Appointments in Howell & Bloomfield Township
Three board-certified podiatric surgeons. 1,123+ five-star reviews. Most insurance accepted.
Hallux rigidus patients sometimes use toe spacers as an adjunct treatment. See our guide: Toe Spacers: Benefits & Limitations — Michigan podiatrist breaks down evidence for toe spacers and who benefits most.
What type of sole is best for hallux rigidus?
A rigid or semi-rigid sole with a forefoot rocker is the most effective footwear modification for hallux rigidus. The rocker geometry allows the foot to roll through the toe-off phase without requiring the big toe joint to bend — the primary source of pain in hallux rigidus. Carbon fiber insole plates provide the stiffness without adding bulk. Look for shoes with a Morton’s extension (stiff insole extending under the big toe) or purchase an aftermarket rigid insole insert. Flexible running shoes and sandals with a bendy forefoot worsen hallux rigidus by forcing the joint through a painful range.
Do rocker-bottom shoes help hallux rigidus?
Yes — rocker-bottom shoes (like Hoka, MBT, or dedicated therapeutic footwear) reduce pain in hallux rigidus for many patients by transferring the pivot point of gait from the 1st MTP joint to the midfoot. The trial evidence is real but more modest than the marketing: in the randomized trial that measured it directly, 39% of people with first MTP joint osteoarthritis reported meaningful improvement after 12 weeks in rocker-sole footwear, compared with 62% of those given prefabricated foot orthoses (Menz et al., BMC Musculoskeletal Disorders, 2017), and a 2024 Cochrane review found no clinically important benefit for shoe-stiffening inserts or arch-contouring orthoses against sham. Rocker soles are worth trying because they reduce how far the joint has to bend, but expect them to help some patients rather than most. For advanced (Grade III-IV) hallux rigidus with bone-on-bone arthritis and no flexible range of motion, footwear modifications still reduce discomfort but are typically combined with cortisone injection or surgical consultation.
When should I see a podiatrist for hallux rigidus?
See a podiatrist if big toe joint pain or stiffness limits walking, worsens with activity, or has lasted more than 4 weeks, limit activity, or you have diabetes or poor circulation. Same-day appointments at Balance Foot & Ankle — (810) 206-1402 — Howell & Bloomfield Township, MI.
For a complete clinical overview: Our Podiatrist-Recommended Shoes Guide — covers podiatrist-approved footwear for every foot condition, with current top picks by category.
Podiatrist Pairing — Best Insole for This Shoe Category
Hallux rigidus (stiff big-toe joint) demands a rigid forefoot to limit dorsiflexion. A firm insole with a Morton extension or rigid forefoot plate dramatically reduces big-toe pain when paired with a stiff-sole shoe. Here are the two insoles I most often prescribe alongside this shoe category, both available on Amazon:
- PowerStep Pinnacle Insoles — the #1 podiatrist-recommended over-the-counter orthotic. Full-length with built-in arch support and a deep heel cradle. Fits inside most shoes after removing the stock insole.
- Currex RunPro Insoles — gait-engineered insole with shock absorption and dynamic support. Three arch profiles (low / med / high) so it matches your actual foot.
Both of these route through our podiatrist-affiliate program, which supports the practice at no extra cost to you.
Book an appointment with a podiatrist
Stiff-soled and rocker-bottom shoes genuinely reduce pain at the big toe joint, and for many people they are enough. Hallux rigidus is arthritis, though, and it progresses — an exam with weight-bearing X-rays establishes how far the joint has changed, which is what decides whether footwear, an orthotic, an injection or something more is the right next step. Balance Foot & Ankle sees patients at two offices — Howell in Livingston County, and Bloomfield Township in Oakland County.
Book online, 24/7: choose a real appointment time at Howell or Bloomfield Township. Prefer to speak with someone first? Call (810) 206-1402 or use the form below.

Dr. Tom Biernacki, DPM is a board-certified foot & ankle surgeon (ABFAS & ABPM) at Balance Foot & Ankle Specialists in Southeast Michigan. With over a decade of clinical experience, he specializes in heel pain, bunions, diabetic foot care, sports injuries, and minimally invasive surgery. Dr. Biernacki is a member of the APMA and ACFAS, and his patient education content on MichiganFootDoctors.com and YouTube has made him one of the most-followed foot & ankle educators on YouTube.
More questions patients ask
What is hallux rigidus and what shoes help?
Hallux rigidus is arthritis of the first metatarsophalangeal (MTP) joint, causing progressive stiffness and pain at the base of the big toe. Shoes with a rocker-bottom sole reduce the need for toe dorsiflexion during push-off, significantly relieving hallux rigidus pain. Brands like Hoka, On, and Dansko are frequently recommended, along with carbon fiber insole plates that limit painful joint motion.
Should I avoid certain shoes with hallux rigidus?
Avoid flexible, flat, or zero-drop shoes that require full big toe extension during walking, as these maximize stress on the arthritic joint. High heels shift weight onto the forefoot and aggravate hallux rigidus. Shoes with thin, flat soles (ballet flats, flip-flops) are also problematic. Instead, choose shoes with rocker soles, stiff footplates, or carbon fiber shanks.
Can hallux rigidus get worse without treatment?
Yes. Untreated hallux rigidus progresses through 4 grades from mild stiffness to complete joint fusion. Each grade corresponds to increasing bone spur formation and cartilage loss. Conservative treatment (appropriate shoes, orthotics, injections) slows progression and manages symptoms. Advanced Grade 3–4 hallux rigidus may require surgery — either joint-preserving procedures or fusion (arthrodesis).
Still have a question about coverage or cost? Book online and we will check your benefits before your visit: Book in Howell · Book in Bloomfield Township. Prefer to talk it through first? Call (810) 206-1402.