

Board-Certified Podiatric Foot & Ankle Surgeon · Last reviewed: May 5, 2026
Quick Answer
Most heel spurs never need surgery. The spur is rarely what hurts, and about 90% of plantar fasciitis cases settle with conservative care within 12 months. When surgery is needed for pain on the bottom of the heel, it is usually a partial plantar fascia release, often endoscopic, and most patients are back in regular shoes in 4–6 weeks. Spurs at the back of the heel are different: they are removed along with a Haglund’s bump when they irritate the Achilles, and it takes about 3–4 months to walk comfortably again.
Most heels offered surgery are really being offered it for the fascia rather than for the spur. Our sister site Heel Guide covers when plantar fasciitis surgery is genuinely considered, and what recovery actually involves.
Watch: Heel Spurs That Won’t Heal
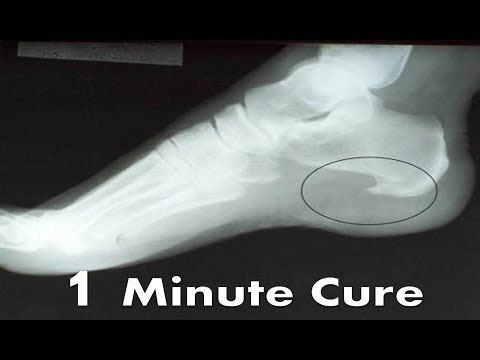
Are Heel Spurs the Real Problem?
Heel spurs—bony calcium deposits that form on the underside (plantar) or back of the heel bone (calcaneus)—are frequently blamed for heel pain. However, research consistently shows that plantar heel spurs are present in approximately 15–25% of the general asymptomatic population. The spur itself rarely causes pain. The actual source of pain in most heel complaints is plantar fasciitis—inflammation of the plantar fascia where it attaches to the heel. For specialized treatment, see our plantar fasciitis treatment Michigan. The spur and the plantar fasciitis often coexist, leading patients to attribute their pain to the spur when the fascia is the actual pain generator.
Posterior heel spurs—located at the back of the heel where the Achilles tendon inserts—are a different entity. These are associated with Haglund’s deformity (a prominent posterosuperior calcaneal bump) and insertional Achilles tendinopathy. Posterior heel spurs can directly cause pain by irritating the Achilles tendon and retrocalcaneal bursa, and they are more directly involved in the pain than plantar spurs.
When Is Surgery Actually Needed?
The vast majority of heel pain—regardless of whether a spur is present—responds to conservative treatment: stretching (plantar fascia and calf), night splints, orthotics or supportive footwear, cortisone injection, and physical therapy. Approximately 90% of plantar fasciitis cases resolve within 12 months with appropriate conservative care. Surgery is considered only when pain remains significant after 6–12 months of diligent, well-executed conservative treatment.
When surgery is performed for persistent plantar heel pain (plantar fasciitis), the primary procedure is plantar fascia release—releasing a portion of the tight, thickened fascia to reduce tension at its insertion. The heel spur itself is generally not removed during this procedure, as it is not the pain source. Removing the spur without addressing the fascial tension provides no benefit and adds unnecessary bone work. Modern minimally invasive plantar fascia release (endoscopic plantar fasciotomy) or ultrasound-guided percutaneous fasciotomy achieves fascial release through very small incisions with good outcomes and faster recovery than open surgery.
Posterior Heel Spur Surgery
For insertional Achilles tendinopathy with posterior heel spur and Haglund’s deformity, surgical treatment involves debridement of the diseased Achilles tendon insertion, removal of the posterosuperior calcaneal prominence (Haglund resection), and removal of the posterior spur. The retrocalcaneal bursa (inflamed bursa between the Achilles and calcaneus) is also removed. When more than 50% of the Achilles insertion must be removed during debridement, augmentation with the flexor hallucis longus (FHL) tendon transfer may be performed to reinforce the repair. Recovery from posterior heel surgery is typically 3–4 months to comfortable walking, with return to sport at 6–12 months.
What to Expect from Plantar Fascia Release
When plantar fascia release is performed (endoscopic or open), patients typically bear weight in a surgical sandal or boot within days of surgery. The procedure is outpatient. Recovery for endoscopic release is generally 4–6 weeks to regular shoe wear and 8–12 weeks to return to sport. Open plantar fascia release may require slightly longer wound healing but achieves comparable pain relief. Success rates (significant reduction in pain) are approximately 75–85%. Risks include nerve injury (medial calcaneal or lateral plantar nerve), plantar fascia rupture (over-release), infection, and—uncommonly—flatfoot development from excessive fascial release. Most surgeons release no more than 30–40% of the plantar fascia to minimize flatfoot risk.
In-Office Treatment at Balance Foot & Ankle
If home care isn’t resolving your heel pain, a visit with a board-certified podiatrist is the fastest path to accurate diagnosis and a personalized plan. At Balance Foot & Ankle Specialists, Dr. Tom Biernacki, Dr. Carl Jay, and Dr. Daria Gutkin offer appointments at both our Howell and Bloomfield Township offices. We perform on-site diagnostic ultrasound, digital X-ray, conservative care, advanced regenerative treatments, and minimally invasive surgery when indicated.
Call (810) 206-1402 or request an appointment online. Most insurance plans accepted, including Medicare, Blue Cross Blue Shield, Aetna, Cigna, and United Healthcare.
Heel Spur Surgery Recovery: Week by Week
Recovery depends on which spur is treated. Surgery on the bottom of the heel (a plantar fascia release, with or without removing the spur) has you walking in a surgical shoe right away. Surgery on the back of the heel (a Haglund’s resection, with the Achilles detached and reattached) needs time off the foot so the tendon can heal.
Plantar fascia release (bottom of the heel)
| Timeframe | What to expect | Activity level |
|---|---|---|
| Week 1–2 | Peak swelling and pain; sutures in place; surgical dressing | Weight bearing in a surgical shoe, heel walking only; elevate and ice often |
| Week 2–4 | Sutures removed; swelling going down; soreness at the incision | Move into a supportive athletic shoe; walk a little more each day |
| Week 4–6 | Most surgical pain gone; some stiffness is common | Normal walking; gentle stretching and physical therapy begin |
| Week 6–12 | Steady improvement; some patients still have mild heel soreness | Most activities; low-impact exercise such as cycling and swimming |
| Month 3–4 | The full benefit of the surgery | Running and high-impact activity |
Haglund’s resection (back of the heel)
| Timeframe | What to expect | Activity level |
|---|---|---|
| Week 1–2 | Splint or cast; significant swelling; pain controlled with medication | No weight on the foot: crutches or a knee scooter |
| Week 2–4 | Sutures removed; into a walking boot | Protected weight bearing in the boot, flat-foot walking only (no push-off) |
| Week 4–8 | Swelling slowly going down; the Achilles repair is healing | More weight in the boot; gentle ankle range-of-motion exercises |
| Week 8–12 | Out of the boot and into supportive shoes with a heel lift | Physical therapy: stretching, strengthening and gait training |
| Month 3–12 | Strength and flexibility keep improving | Comfortable walking by months 3–4; running and sports usually take 6–12 months |
What to Expect After Surgery
Pain: The first 3–5 days are the most uncomfortable, and your surgeon will prescribe pain medication for that period. After the first week most patients switch to over-the-counter acetaminophen or ibuprofen. A long-acting local anesthetic block given during surgery can greatly reduce the pain of the first day or two.
Swelling: The foot swells a lot, especially in the first 2 weeks. Keeping it above heart level and icing it (20 minutes on, 20 minutes off) matter more than anything else. Some swelling can last 2–3 months; that is normal and fades gradually.
Driving: After surgery on the right foot, plan on no driving for 4–6 weeks after a plantar fascia release or 6–10 weeks after a Haglund’s resection. After left-foot surgery you may drive sooner if your car is an automatic.
Work: Desk jobs can usually resume at 1–2 weeks from home or 2–4 weeks in the office. Jobs with a lot of standing or walking may need 6–12 weeks off, depending on the procedure.
Tips for a faster recovery
- Follow the weight-bearing plan exactly. Putting weight on the foot too early, especially after an Achilles reattachment, can make the repair fail.
- Elevate in the first 2 weeks. Keep the foot above heart level as much as you can; it reduces swelling more than any other single habit.
- Start physical therapy when you are cleared. It restores motion, strength and a normal walk, and calf and plantar fascia stretching helps keep the problem from coming back.
- Wear orthotics once you are back in regular shoes. The foot mechanics that caused the problem are still there after surgery.
Warning signs after surgery: call your surgeon
- Pain that is getting worse after day 5 (it should be improving)
- Redness, warmth or drainage from the incision, which can mean infection
- Fever above 101°F (38.3°C)
- Calf pain or swelling, which can mean a blood clot (DVT): get seen right away
- New numbness that was not there before surgery
- A sudden pop or loss of push-off strength after Haglund’s surgery, which can mean the Achilles repair has failed
What to Wear While You Recover
Once your surgeon lets you out of the surgical shoe or boot, an open-back recovery slide is an easy first shoe: it cushions the heel without pressing on an incision at the back of the heel. Wear it around the house and for short outings until you are cleared for regular shoes, then move to supportive shoes with an arch support or orthotic.

As an Amazon Associate, Balance Foot & Ankle earns from qualifying purchases.
Differential Diagnosis: What Else Could It Be?
Before any heel surgery, these causes of heel pain need to be ruled out, because they need different treatment. Considering these alternatives is part of every Balance Foot & Ankle exam:
- Baxter’s nerve entrapment. Compressed first branch of lateral plantar nerve — burning medial heel pain rather than first-step sharpness.
- Calcaneal stress fracture. Squeeze test of the heel reproduces pain anywhere; PF is reproduced only at the medial-plantar attachment.
- Heel spur (incidental). Spurs show on X-ray but rarely cause pain on their own — treat the fascia, not the spur.
If your symptoms don’t fit the textbook pattern, ask your podiatrist which differentials they ruled out — that conversation often shortcuts months of trial-and-error treatment.
Warning Signs That Need Same-Day Care
Seek immediate evaluation at Balance Foot & Ankle if you experience any of the following:
- Unable to bear weight on the heel
- Bruising or visible swelling around the heel
- Constant rest or night pain in the heel
- No improvement after 6 weeks of home care
Call (810) 206-1402 — appointments at our Howell and Bloomfield Township offices.
Medical References & Sources
- American Orthopaedic Foot & Ankle Society — Heel Pain
- PubMed Research — Plantar Fascia Release Outcomes
- PubMed Research — Haglund Resection Outcomes
Dr. Tom Biernacki, DPM is a board-certified podiatric surgeon at Balance Foot & Ankle in Howell and Bloomfield Township, Michigan. He treats plantar heel pain and insertional Achilles tendinopathy with conservative management and minimally invasive surgical options including endoscopic plantar fascia release and Haglund resection.
Ready to Get Back on Your Feet?
Appointments in Howell + Bloomfield Township. Most insurance accepted. Dr. Tom Biernacki, DPM & team.
Book Today — Online Booking 24/7 Available
Call Now: (810) 206-1402
Frequently Asked Questions
Are heel spurs painful?
Heel spurs themselves are not the primary source of pain in most cases. About 70% of people with plantar fasciitis have a heel spur on X-ray, but heel spurs are also found in 15–25% of adults with no heel pain. The pain comes from plantar fascia inflammation at the heel attachment, not from the spur scraping tissue. This is why removing the spur surgically rarely changes outcomes — the fascia degeneration is the underlying problem that drives the pain.
What’s the difference between a heel spur and plantar fasciitis?
Plantar fasciitis is inflammation and degeneration of the plantar fascia ligament at its heel attachment — the most common cause of heel pain. A heel spur is a bony calcium deposit that forms on the bottom of the heel bone. The two frequently coexist, and the spur forms as the body’s response to chronic fascial tension at the heel. Treating the plantar fasciitis resolves the pain in the vast majority of cases; the spur remains on X-ray but becomes asymptomatic.
Does a heel spur require surgery?
Rarely. Heel spur surgery is indicated only when conservative treatment has failed for 6–12 months and the specific spur is confirmed as the pain source — not the fascia. This applies to perhaps 2–3% of heel spur cases. Modern surgery is usually an endoscopic or minimally invasive plantar fascia release, sometimes with removal of a large spur; most patients are back in regular shoes in 4–6 weeks. In our practice, we counsel strongly against spur removal as an isolated procedure because removing the spur without addressing the underlying fascial pathology produces unpredictable outcomes.
How is a heel spur diagnosed?
X-ray confirms the presence and size of a heel spur. A heel spur appears as a bony projection on the calcaneus (heel bone) visible on a lateral foot X-ray. However, finding a spur on X-ray doesn’t confirm it’s causing symptoms — the clinical examination (point tenderness, gait analysis, response to treatment) is equally important. Ultrasound and MRI are used when soft tissue pathology alongside the spur (fascia thickening, partial tears) needs characterization.
Can heel spurs go away on their own?
Bone doesn’t resorb spontaneously in adults without a pathological process. Once a heel spur forms, it’s permanent — but it becomes asymptomatic in the vast majority of patients who treat the underlying plantar fasciitis. The goal isn’t to eliminate the spur; it’s to resolve the fascial inflammation that made it painful in the first place. When the fascia heals, the spur is still there but no longer provokes a pain response.
What treatments work for heel spur pain?
Treatment is essentially identical to plantar fasciitis treatment: daily stretching (plantar fascia and calf), supportive footwear with heel elevation, custom or OTC orthotics, night splints, and activity modification. For persistent cases: corticosteroid injection, shockwave therapy, and PRP. These target the plantar fascia inflammation, not the spur directly — which is appropriate because the fascia is the pain generator. We start with the least invasive options and escalate based on response.
What is posterior heel spur vs. inferior heel spur?
Inferior (bottom) heel spurs form at the plantar fascia attachment on the bottom of the heel and are associated with plantar fasciitis. Posterior heel spurs form at the Achilles tendon insertion on the back of the heel and are associated with Haglund’s deformity (pump bump) and insertional Achilles tendinopathy — a completely different condition requiring different treatment. Both show up on X-ray but are in distinct anatomical locations; the clinical exam identifies which is causing symptoms.
Does shock wave therapy work for heel spurs?
Extracorporeal shockwave therapy (ESWT) shows 60–75% success rates for chronic plantar fasciitis and heel spur pain that has not responded to 6+ months of conservative care. It delivers acoustic pressure waves that stimulate healing and reduce nerve sensitization. Treatment consists of 3–5 sessions over 3–5 weeks; results appear over 6–12 weeks. It’s non-invasive, requires no anesthesia, and has minimal downtime. We offer ESWT in-office as a step between conservative care and surgery.
Can a heel spur grow back after surgery?
It can, but it is uncommon if the cause is addressed. A spur forms from chronic pulling on the heel bone; if you go back to unsupportive shoes and skip orthotics after surgery, the same forces can build a new one over time. That is why orthotics and good footwear after recovery matter so much for long-term success.
How painful is heel spur surgery?
It depends on the procedure. A plantar fascia release is the smaller operation: most patients need prescription pain medication for 3–5 days, then switch to over-the-counter options. A Haglund’s resection with Achilles reattachment involves bone and tendon work, so plan on 5–7 days of prescription pain control. In both cases the surgical pain is usually less than the chronic heel pain that led to surgery.

Dr. Tom Biernacki, DPM is a board-certified foot & ankle surgeon (ABFAS & ABPM) at Balance Foot & Ankle Specialists in Southeast Michigan. With over a decade of clinical experience, he specializes in heel pain, bunions, diabetic foot care, sports injuries, and minimally invasive surgery. Dr. Biernacki is a member of the APMA and ACFAS, and his patient education content on MichiganFootDoctors.com and YouTube has made him one of the most-followed foot & ankle educators on YouTube.