
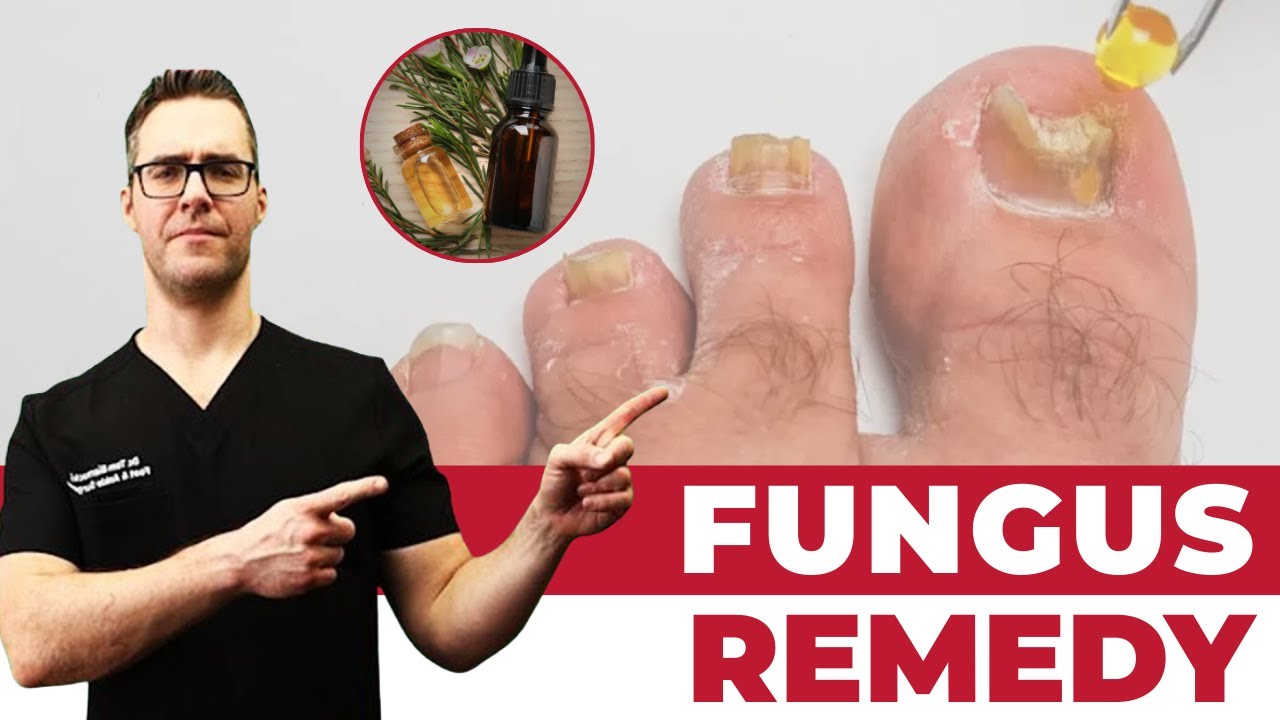
Watch: Tea Tree Oil Toenail Fungus Home Treatment [Doctor Cure!] — MichiganFootDoctors YouTube
Medically reviewed by Dr. Tom Biernacki, DPM
Board-certified podiatric surgeon | Balance Foot & Ankle
Last reviewed: April 2026
This is one of the most common diagnostic challenges in podiatry: a patient presents with thickened, discolored toenails. The obvious answer is toenail fungus — it’s extremely common and everyone has heard of it. But a significant subset of these cases is actually nail psoriasis, which requires completely different treatment.
Getting this diagnosis wrong means months of antifungal treatment that won’t work, continued nail damage, and delayed treatment for an underlying autoimmune condition. This guide shows you how to tell the difference — and what to expect from the correct treatment.
The most important clinical decision with Nail Fungus Vs Nail Psoriasis isn’t which treatment to start with — it’s identifying the correct subtype. That changes everything. Call (810) 206-1402.
Why This Distinction Matters

Onychomycosis (toenail fungus) is treated with antifungal medications: topical (ciclopirox, efinaconazole, tavaborole) for mild cases, oral (terbinafine for 12 weeks) for moderate-severe, or laser therapy. None of these work on nail psoriasis.
Nail psoriasis is an autoimmune condition where the immune system attacks the nail matrix and nail bed. Treatment involves topical corticosteroids or calcineurin inhibitors applied to the nail fold, intralesional steroid injections, biologics for patients with psoriatic arthritis, and systemic medications like methotrexate. None of these treat fungal infection.
Adding to the complexity: both conditions can coexist in the same patient. Psoriatic nails are more susceptible to fungal infection because onycholysis (nail lifting) creates a warm, moist environment where fungi thrive. Studies show that 13–27% of patients with nail psoriasis also have onychomycosis. This is why nail testing is so important.
Nail Fungus (Onychomycosis): Characteristics
Onychomycosis affects approximately 10% of the general population and up to 50% of people over 70. It is caused most commonly by Trichophyton rubrum (responsible for ~80% of cases), with other dermatophytes, Candida, and non-dermatophyte molds accounting for the remainder.
- Color: yellow, white, or brown — often yellow-white at the distal edge, spreading proximally
- Location: starts at the distal (tip) edge and progresses toward the nail base
- Texture: nail plate thickens, becomes crumbly or powdery, may crumble away entirely
- Subungual debris: yellow-brown powdery material accumulates under the nail
- Separation: nail lifts from the nail bed (onycholysis) as infection progresses
- Odor: may be present from bacterial co-infection
- Involvement: typically asymmetric; may spread to involve multiple nails over time
- Associated skin findings: athlete’s foot (tinea pedis) is present in majority of patients
Nail Psoriasis: Characteristics
Nail involvement occurs in approximately 80–90% of patients with plaque psoriasis at some point in their disease course, and in 5–10% of patients as isolated nail disease without skin involvement. This isolated nail psoriasis is particularly easy to miss.
- Pitting: small, ice-pick-like indentations across the nail plate surface — hallmark of psoriasis
- Oil drop discoloration: salmon-pink or orange-brown patches visible through the nail plate, not at the tip
- Onycholysis: nail lifting from the nail bed — but with a characteristic red-brown border (the ‘erythematous border’ or ‘salmon border’) at the separation zone
- Subungual hyperkeratosis: buildup of scale under the nail, similar to fungus but often with silvery-white rather than brown color
- Splinter hemorrhages: thin red-brown lines running longitudinally under the nail
- Leukonychia: white patches within the nail plate
- Crumbling: nail plate may crumble, similar to onychomycosis
- Multiple nails: typically affects multiple nails simultaneously, including fingernails
Key takeaway: The three findings most specific for nail psoriasis (not seen in fungus): nail pitting, oil drop (salmon) discoloration, and a red border at the nail separation zone. If any of these are present, nail fungus culture should still be done, but psoriasis is the primary diagnosis until proven otherwise.
How to Definitively Diagnose Each Condition
Clinical examination alone is insufficient to distinguish nail fungus from nail psoriasis in many cases. Laboratory testing is essential:
For Onychomycosis
- KOH preparation: nail clippings dissolved in potassium hydroxide and examined under microscopy for fungal hyphae; fast but operator-dependent, misses 30–40% of cases
- Fungal culture: nail clippings cultured on Sabouraud’s agar; gold standard but takes 2–6 weeks; identifies specific organism and guides treatment choice
- PAS stain (periodic acid-Schiff): nail biopsy tissue stained; very sensitive but requires biopsy
- PCR testing: rapid, highly sensitive and specific; becoming more widely available; identifies organism and antifungal resistance
For Nail Psoriasis
- Dermatoscopy (dermoscopy): handheld microscope reveals characteristic psoriatic patterns — pitting, oil drops, salmon color — with high specificity
- Nail biopsy: definitive; shows psoriatic histopathology (parakeratosis, dilated tortuous capillaries in the nail bed)
- Clinical context: skin psoriasis elsewhere, personal or family history, psoriatic arthritis (joint symptoms)
- Negative fungal culture: supports psoriasis diagnosis but does not confirm it (culture can be negative in mild fungal infection too)
When Both Are Present
In patients with nail psoriasis and concurrent onychomycosis, both must be treated simultaneously. Our approach:
- Confirm fungal infection with culture before initiating antifungal therapy
- Treat fungal infection with appropriate antifungal (usually oral terbinafine for 12 weeks)
- Simultaneously treat psoriasis with topical corticosteroid under nail fold + calcipotriol nail lacquer
- Consider biologics for patients with concurrent psoriatic arthritis
- Monitor both conditions; reassess culture at completion of antifungal course
Treatment Comparison
Treating Nail Fungus
- Oral terbinafine: 250 mg/day × 12 weeks for toenails; most effective oral agent (~76% mycologic cure)
- Oral itraconazole: pulse dosing (400 mg/day × 1 week/month × 3 pulses)
- Topical efinaconazole (Jublia) or tavaborole (Kerydin): applied daily for 48 weeks; mild-moderate disease
- Laser therapy: available in our office; no systemic side effects; growing evidence base
- Ciclopirox lacquer: older topical; moderate efficacy for mild disease
Treating Nail Psoriasis
- Topical corticosteroid: high-potency (clobetasol 0.05%) applied to the nail fold and under the nail plate
- Calcipotriol: vitamin D analog applied to the nail fold
- Intralesional triamcinolone: injection into the nail matrix — effective but painful
- Biologics (adalimumab, secukinumab, ixekizumab): highly effective for nail psoriasis, especially with psoriatic arthritis
- Systemic agents: methotrexate, apremilast for widespread psoriasis
In-Office Treatment at Balance Foot & Ankle
If home treatment isn’t providing relief for your nail fungus vs nail psoriasis, our podiatry team at Balance Foot & Ankle can help with same-day evaluations and advanced in-office care.
Same-day appointments available. (810) 206-1402
Learn about our toenail fungus laser treatment → | Book online →
Doctor Hoy’s Natural Pain Relief Gel
Natural topical pain relief I use in our clinic. Arnica + camphor formula — apply directly to the area 3–4x daily. ($20–25)
Shop Doctor Hoy’s →Frequently Asked Questions: Nail Fungus vs Nail Psoriasis
Can you tell nail fungus from psoriasis just by looking?
Often not reliably — the conditions can look nearly identical. Nail pitting is more specific to psoriasis; distal yellow-brown crumbling starting at the tip is more specific to fungus. But many cases require laboratory testing to distinguish them. A podiatrist or dermatologist with dermoscopy and access to nail culture testing makes the most accurate diagnosis.
How long does nail psoriasis treatment take?
Nail psoriasis is slow to respond — nails grow slowly and the nail matrix needs time to produce healthier plate. Topical treatments typically show improvement after 3–6 months and may require 12+ months for full response. Biologic medications (for patients with systemic psoriasis or psoriatic arthritis) often produce more rapid and dramatic improvement, sometimes within 3–4 months.
Does nail psoriasis spread to other people?
No — nail psoriasis is an autoimmune condition, not an infection. It cannot be transmitted to others. Nail fungus, however, is contagious — it can spread from person to person via shared footwear, pedicure equipment, or communal shower floors. This is another reason accurate diagnosis matters.
Should I get a nail biopsy?
Nail biopsy is the most definitive test for nail psoriasis diagnosis but is invasive. We typically start with nail clipping culture (to rule out or confirm fungus) and dermatoscopy. If culture is repeatedly negative, clinical features suggest psoriasis, and the patient has not responded to antifungal therapy, nail biopsy confirms the diagnosis and guides further treatment.
Can nail psoriasis be cured?
Nail psoriasis is a chronic autoimmune condition — it can be controlled but not permanently cured in most patients. Many patients achieve nail clearance or near-clearance with biologics. When the medication is stopped, psoriasis typically recurs. Continuous or intermittent long-term therapy is often required for sustained nail improvement.
Sources
- Starace M, et al. Nail Psoriasis: An Updated Review and Expert Opinion on Available Treatments. Drugs. 2020;80(11):1113–1133.
- Piraccini BM, Alessandrini A. Onychomycosis: A Review. J Fungi. 2015;1(1):30–43.
- Rigopoulos D, et al. Nail Psoriasis: A Combined Treatment Approach. J Eur Acad Dermatol Venereol. 2024;38(1):96–104.
- Gupta AK, et al. Onychomycosis in 2024: An Update on Epidemiology, Diagnosis, and Treatment. J Am Acad Dermatol. 2024;91(1):38–51.
- Dogra A, Arora AK. Nail Psoriasis: The Journey So Far. Indian J Dermatol. 2014;59(4):319–333.
Ready to Get Expert Foot Care?
Same-day appointments available in Howell & Bloomfield Township, MI
4.9★ | 1,123 Reviews | 3,000+ Surgeries
Or call: (810) 206-1402

Dr. Tom Biernacki, DPM is a board-certified foot & ankle surgeon (ABFAS & ABPM) at Balance Foot & Ankle Specialists in Southeast Michigan. With over a decade of clinical experience, he specializes in heel pain, bunions, diabetic foot care, sports injuries, and minimally invasive surgery. Dr. Biernacki is a member of the APMA and ACFAS, and his patient education content on MichiganFootDoctors.com and YouTube has made him one of the most-followed foot & ankle educators on YouTube.