
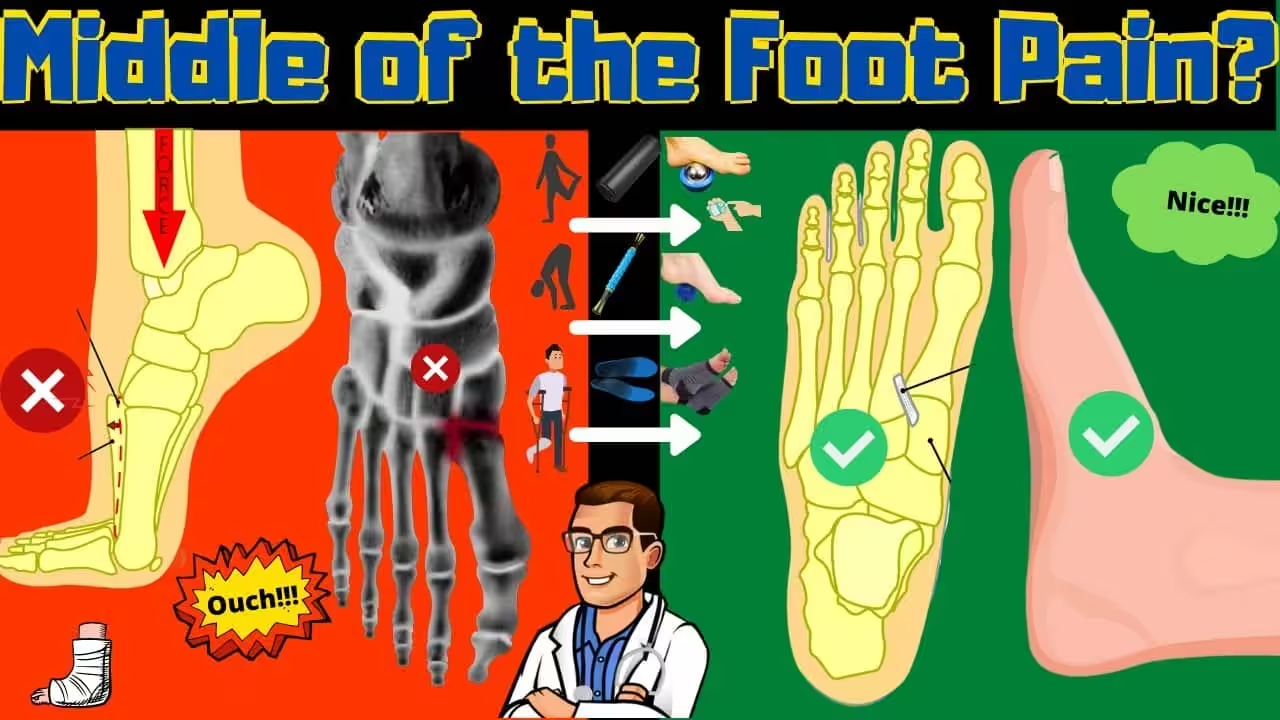

You are in the right place. Dr. Tom Biernacki, DPM, FACFAS — board-certified foot & ankle surgeon — explains exactly what Lisfranc injury recovery means and what actually works. Call (810) 206-1402 for an appointment at our Howell or Bloomfield Township office.
Ready to be seen? Book a real appointment time online, 24/7 — Howell or Bloomfield Township. Takes about a minute, 24/7.
In This Article
- What a Lisfranc Injury Actually Is
- Symptoms and Diagnosis
- Types of Lisfranc Injuries
- Lisfranc Treatment Options
- Lisfranc Recovery Timeline by Injury Type
- Surgical Recovery: What to Expect Week by Week
- Rehabilitation After Lisfranc Injury
- Products That Support Lisfranc Recovery
- Lisfranc Treatment at Balance Foot & Ankle
- Frequently Asked Questions
- Sources
A Lisfranc injury is one of the most misdiagnosed and undertreated injuries in foot and ankle surgery. Patients frequently leave emergency departments with a diagnosis of “midfoot sprain,” only to return months later with persistent midfoot pain, arch collapse, and progressive arthritis — all because the Lisfranc ligament complex injury was missed on initial X-ray. If you have been told you have a midfoot sprain and are not improving as expected, keep reading.
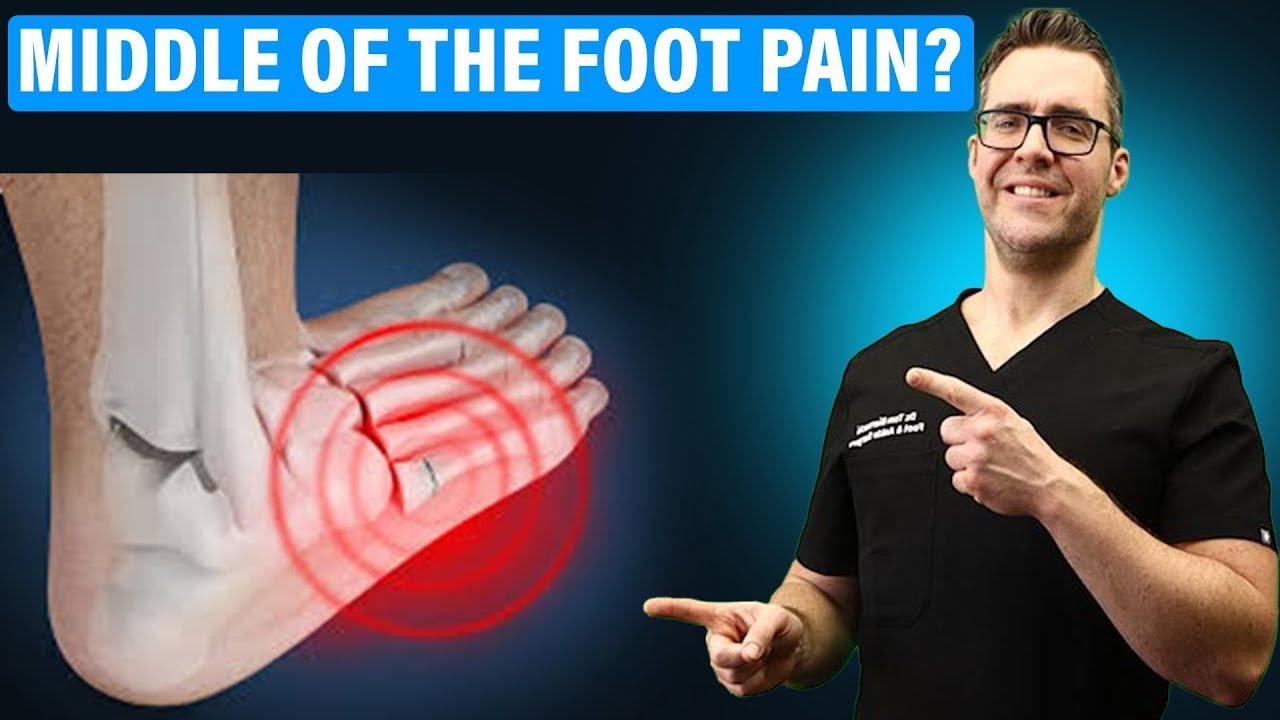
What a Lisfranc Injury Actually Is
The Lisfranc joint complex is the articulation between the midfoot (cuneiforms and cuboid) and the metatarsals — the five bones that form the ball of your foot. The Lisfranc ligament specifically connects the medial cuneiform to the base of the second metatarsal, acting as the keystone that locks the entire transverse arch. When this ligament tears — with or without associated fractures — the structural integrity of the midfoot is compromised.
In our clinic, we see Lisfranc injuries most often from three mechanisms: direct crush injuries (a heavy object dropped on the foot), axial loading with the foot plantarflexed (the classic equestrian injury — foot caught in stirrup during a fall), and low-energy twisting injuries that can look benign but carry significant Lisfranc disruption. The low-energy mechanism is the most dangerous diagnostically because it does not produce the dramatic swelling and deformity of high-energy injuries, and is frequently dismissed as a routine sprain.
Lisfranc Injury Symptoms and Diagnosis
A Lisfranc injury often feels like a bad sprain at first. These signs point to the Lisfranc joint instead:
- Pain and swelling on the top of the midfoot that is worse when you stand, walk or push off.
- Bruising on the sole of the foot in the arch (plantar ecchymosis), often showing up a day or two after the injury. This is a classic warning sign of a Lisfranc tear.
- Trouble rising onto your toes. Being unable to do a single-leg heel rise on the injured side suggests the midfoot is not stable.
- Difficulty putting weight on the foot, or a foot that looks wider or flatter than the other one.
The exam presses along the joints where the midfoot meets the metatarsals and compares both feet. Imaging then answers the key question, which is whether the joint is stable:
- Weight-bearing X-rays of both feet. Standing loads the joint and can open a gap that an X-ray taken lying down hides. A gap of more than 2 mm between the medial cuneiform and the base of the second metatarsal, compared with the other foot, means the joint is unstable.
- The “fleck sign.” A tiny chip of bone pulled off where the Lisfranc ligament attaches shows that the ligament has torn away.
- MRI when the X-rays look normal but the exam still suggests a Lisfranc injury. It shows the ligament itself.
- CT scan to map fractures in detail and plan surgery.
If you were told you had a midfoot sprain after X-rays taken lying down, and you are not clearly better after two to three weeks, ask for weight-bearing views. Our guide to telling a Lisfranc sprain from a fracture walks through the differences.

Types of Lisfranc Injuries
Lisfranc injuries are classified by the Myerson classification, which guides treatment decisions and shapes recovery expectations significantly.
| Type | Description | Stability | Treatment |
|---|---|---|---|
| Sprain (Partial Tear) | Partial Lisfranc ligament tear, no diastasis on stress X-ray | Stable | Non-weight-bearing cast or boot 6–8 weeks, then protected walking |
| Type A (Total Incongruity) | Complete dislocation of all five metatarsals in same direction | Unstable | ORIF or primary arthrodesis |
| Type B (Partial Incongruity) | One or more metatarsals displaced, others intact | Unstable | ORIF |
| Type C (Divergent) | Metatarsals displace in opposite directions, severe ligament disruption | Highly Unstable | ORIF or primary arthrodesis |
The critical decision point in Lisfranc management is whether the injury is stable or unstable. This is determined by weight-bearing X-rays — standard non-weight-bearing films will often appear normal even with significant ligament disruption. If your X-rays were taken lying down in the ER, you may not have received a complete assessment. Weight-bearing views with >2mm diastasis (gap) between the medial cuneiform and second metatarsal base confirm instability and require surgical management.
Lisfranc Treatment Options
Treatment follows from one question: is the joint stable on weight-bearing X-rays?
- Stable sprain: no surgery. A cast or boot with no weight on the foot, then a gradual return to walking. See treating a stable Lisfranc sprain without surgery.
- Unstable injury or fracture-dislocation: surgery. Open reduction and internal fixation (ORIF) holds the joints in position with screws or a plate; a primary fusion permanently joins the damaged joints. See Lisfranc injury surgery: when it is needed and what to expect.
- Why a small gap matters. The anatomy of the Lisfranc joint explains why even 2 mm of shift changes the treatment.
- Arthritis years later. A midfoot that becomes stiff and painful long after the injury may have post-traumatic arthritis; see midfoot arthritis of the Lisfranc joint.
Lisfranc Recovery Timeline by Injury Type
Recovery timelines for Lisfranc injuries vary more than almost any other foot injury, which is why patients are often confused when their “sprain” takes far longer to heal than expected.
Stable Lisfranc Sprain (Partial Tear): 6–8 weeks non-weight-bearing in a cast or boot, followed by gradual transition to weight-bearing over 4–6 weeks. Full return to sport: 4–6 months. Some patients with significant sprains develop midfoot pain for up to a year. Persistent pain beyond 6 months warrants re-evaluation for subtle instability or early post-traumatic arthritis.
Surgical ORIF (Plates and Screws): 6–8 weeks non-weight-bearing in cast, then 4–6 weeks in a CAM walker. Hardware removal at about 4–6 months (screws crossing mobile joints). Physical therapy begins at 3 months. Return to sport: typically 9–12 months. Return to heavy labor: 12–18 months.
Primary Arthrodesis (Fusion): For severe injuries or patients over 50 with pre-existing arthritis, primary fusion of the medial Lisfranc joints (first, second, third TMT joints) produces more reliable long-term outcomes than ORIF. Recovery is similar to ORIF at 6–8 weeks non-weight-bearing, but return to activity may be slightly slower at 12–18 months due to fusion healing requirements.
The most common mistake we see is putting weight on the midfoot before the Lisfranc ligament complex has healed. Loading it too early can leave the joint permanently unstable and speeds up midfoot arthritis, so patience here is non-negotiable.
Surgical Recovery: What to Expect Week by Week
Surgical Lisfranc recovery is a structured progression — deviation from the protocol in either direction (too fast or too slow) leads to complications. Here is what we walk our patients through in our clinic.
Weeks 0–2 (Acute Phase): Posterior splint or cast, strict non-weight-bearing on crutches or knee scooter. Limb elevation above heart level as much as possible. Ice 20 minutes on/off for swelling control. Follow-up X-rays at 2 weeks to confirm hardware position.
Weeks 2–8 (Immobilization Phase): Transition to fiberglass cast, continue strict non-weight-bearing. Many patients underestimate the difficulty of this phase — 6–8 weeks on crutches or a knee scooter for an otherwise healthy adult is genuinely exhausting. A knee scooter is strongly preferred over crutches for most patients to preserve energy and reduce upper body strain.
Weeks 8–16 (Transition Phase): CAM walker boot, gradual progressive weight-bearing beginning at 25% and advancing weekly. No impact activities. Pool walking or pool therapy is often initiated here to allow cardiovascular recovery while protecting the repair. The first steps weight-bearing after months off are emotionally significant for patients — do not rush them.
Most of this recovery happens inside a walking boot, and the boot itself is the part people are least prepared for. We have collected the practical tips for wearing one – fit, sleeping, showering, and keeping the other hip level – on a separate page.
Week 16+ (Rehabilitation Phase): Supportive athletic footwear with orthotic support. Physical therapy for range of motion, proprioception, and progressive strengthening. Return to sport protocols beginning at month 6 for most patients. For specific shoe models, see best shoes after a Lisfranc injury on Podiatrist Tested, our sister review site.
Rehabilitation After Lisfranc Injury
Rehabilitation after a Lisfranc injury must address three specific deficits that develop during the non-weight-bearing period: midfoot mobility loss, intrinsic foot muscle atrophy, and proprioceptive impairment. A generic ankle sprain protocol does not address these adequately. In our clinic, we coordinate with physical therapists who specialize in post-surgical foot and ankle recovery and use a Lisfranc-specific progression.
Key rehabilitation milestones: (1) Full pain-free single-leg heel rise by month 4–5 (the heel rise tests the entire midfoot power transmission chain); (2) Normal gait pattern without antalgic limp by month 4; (3) Return to uneven surface walking without instability by month 5; (4) Return to running by month 6–9 for ORIF patients. Midfoot stiffness is expected and normal — the midfoot Lisfranc joints are not designed for significant motion, and post-operative stiffness is generally well-tolerated functionally.
- Increasing midfoot pain after a period of improvement (hardware failure or nonunion)
- Plantar bruising (Lisfranc sign) appearing days after midfoot injury — diagnostic red flag for Lisfranc tear
- Widening or gap between first and second toe bases on X-ray (diastasis)
- Progressive arch collapse or flatfoot deformity developing after injury
- Hardware pain or palpable screw prominence at 3+ months post-op
- Fever, increasing redness, or drainage from surgical incision (infection)
Products That Support Lisfranc Recovery
Midfoot and ankle swelling is a persistent challenge throughout Lisfranc recovery — often lasting 6–12 months post-operatively. DASS graduated compression socks reduce dependent edema by improving venous return, reducing the chronic swelling that limits rehabilitation progress and causes discomfort in footwear. We recommend starting compression as soon as the cast comes off and continuing through the full rehabilitation period.
Not Ideal For: Active peripheral arterial disease. Confirm circulation status before use post-surgically if any vascular concern exists.
Shop DASS Compression at MFDAfter Lisfranc reconstruction, the medial longitudinal arch requires external support to reduce stress on the healing midfoot complex. PowerStep Pinnacle Maxx insoles provide firm arch and heel support that transfers midfoot loading away from the reconstructed Lisfranc joint line. In our practice, we recommend transitioning to PowerStep insoles when patients move from the CAM boot to athletic footwear at 3–4 months post-op, as a bridge to custom orthotic fabrication if needed long-term.
Not Ideal For: Immediate post-surgical phase (boot phase). Use when cleared to full weight-bearing in shoes.
Shop PowerStep at MFDLisfranc Treatment at Balance Foot & Ankle
Lisfranc injuries demand experienced surgical management. The technical demands of ORIF reduction and fixation — achieving anatomic alignment of up to five tarsometatarsal joints while under fluoroscopic guidance — require a surgeon with specific foot and ankle training. Dr. Tom Biernacki has performed this surgery extensively and manages the full spectrum from acute fracture-dislocations to late-presenting Lisfranc arthritis requiring salvage fusion. If you were told you have a “midfoot sprain” months ago and are still not improving, come see us — a delayed Lisfranc diagnosis is still treatable.
Appointments at our Howell and Bloomfield Township offices. Balance Foot & Ankle — 4.9 stars, 1,123+ reviews.
Book Online (810) 206-1402Howell: 4330 E Grand River Ave · Bloomfield Township: 43494 Woodward Ave #208
Frequently Asked Questions
How do I know if I have a Lisfranc injury vs a midfoot sprain?
A plantar ecchymosis (bruising on the sole of the foot at the arch) in the days after a midfoot injury is a classic sign of Lisfranc disruption. Inability to perform a single-leg heel rise is another. Weight-bearing X-rays showing >2mm diastasis between the medial cuneiform and second metatarsal base confirms the diagnosis. If you were seen in an ER and only had lying-down X-rays, follow up with a podiatrist for weight-bearing views.
Can you walk on a Lisfranc injury?
Not until it has been checked. Walking on an unstable Lisfranc injury can shift the joint further out of place and turn a treatable injury into one that needs surgery. Until weight-bearing X-rays show the midfoot is stable, we keep weight off the foot in a boot, with crutches or a knee scooter.
Can a Lisfranc injury heal without surgery?
Stable Lisfranc sprains (partial tears with no diastasis on weight-bearing X-rays) can heal without surgery with 6–8 weeks of strict non-weight-bearing in a cast or boot, followed by 4–6 weeks of protected walking. Unstable injuries — with >2mm diastasis or any displacement on stress views — cannot heal anatomically without surgical fixation and will develop post-traumatic midfoot arthritis if treated conservatively.
When can I walk after Lisfranc surgery?
Most surgically repaired Lisfranc injuries require 6–8 weeks of strict non-weight-bearing on crutches or a knee scooter, followed by 4–6 weeks of progressive weight-bearing in a CAM boot. Most patients are walking in supportive shoes by 3–4 months post-operatively. Return to full activity takes 9–12 months.
Can a Lisfranc injury be misdiagnosed?
Yes, often. It is regularly mistaken for an ordinary midfoot or ankle sprain, especially when the first X-rays were taken lying down. If your “sprain” is not clearly improving after two to three weeks, or you have bruising on the sole of the foot, ask for weight-bearing X-rays.
What happens if a Lisfranc injury is not treated?
An unstable injury that is left alone tends to heal out of position. That leads to chronic midfoot pain, a collapsing arch and arthritis of the midfoot joints, which may eventually need a fusion. Early treatment gives the best chance of a stable, comfortable foot.
What causes long-term problems after a Lisfranc injury?
Post-traumatic midfoot arthritis is the most common long-term complication, affecting roughly a quarter to half of patients with a significant Lisfranc injury in the years afterward, even with good treatment. It manifests as progressively worsening midfoot pain, stiffness, and difficulty with push-off. When conservative management fails, midfoot fusion (arthrodesis) of the involved joints provides reliable pain relief.
Does insurance cover Lisfranc surgery?
Yes — Lisfranc ORIF and arthrodesis are covered by Medicare and most major insurance plans when medically indicated (documented instability on imaging). Pre-authorization is usually required. Our office handles the authorization process and will coordinate with your insurance prior to scheduling.
Sources
- Myerson MS. The diagnosis and treatment of injuries to the Lisfranc joint complex. Orthop Clin North Am. 1989;20(4):655–664.
- Kuo RS, et al. Outcome after open reduction and internal fixation of Lisfranc joint injuries. J Bone Joint Surg Am. 2000;82(11):1609–1618.
- Ly TV, Coetzee JC. Treatment of primarily ligamentous Lisfranc joint injuries: primary arthrodesis compared with open reduction and internal fixation. A prospective, randomized study. J Bone Joint Surg Am. 2006;88(3):514–520.
- Stavlas P, et al. The role of reduction and internal fixation of Lisfranc fracture-dislocations: a systematic review of the literature. Int Orthop. 2010;34(8):1083–1091.
- Sheibani-Rad S, et al. Arthrodesis versus ORIF for Lisfranc fractures. Orthopedics. 2012;35(6):e868–e873.
- Balance Foot & Ankle. Foot Fracture Treatment — Dr. Tom Biernacki DPM.
OrthoInfo – AAOS: Lisfranc Midfoot Injury
Get Expert Care at Balance Foot & Ankle
Appointments at our Howell and Bloomfield Township offices. Most insurance accepted.

Dr. Tom Biernacki, DPM is a board-certified foot & ankle surgeon (ABFAS & ABPM) at Balance Foot & Ankle Specialists in Southeast Michigan. With over a decade of clinical experience, he specializes in heel pain, bunions, diabetic foot care, sports injuries, and minimally invasive surgery. Dr. Biernacki is a member of the APMA and ACFAS, and his patient education content on MichiganFootDoctors.com and YouTube has made him one of the most-followed foot & ankle educators on YouTube.