


Medically reviewed by Dr. Tom Biernacki, DPM · Board-Certified Podiatric Surgeon · Last reviewed: April 2026 · Editorial Policy
Quick Answer
Bone infection in the foot may show as a wound that will not heal, deep persistent pain, swelling, or the ability to probe to bone. Confirmation needs imaging and culture, and treatment is antibiotics with surgery when infected bone is present. Appointments in Howell + Bloomfield Township: (810) 206-1402.
Medically reviewed by Dr. Tom Biernacki, DPM — Board-Certified Podiatric Surgeon — Balance Foot & Ankle, Howell & Bloomfield Township, MI. Last updated April 2026.
▶ Watch
What Is Osteomyelitis of the Foot?
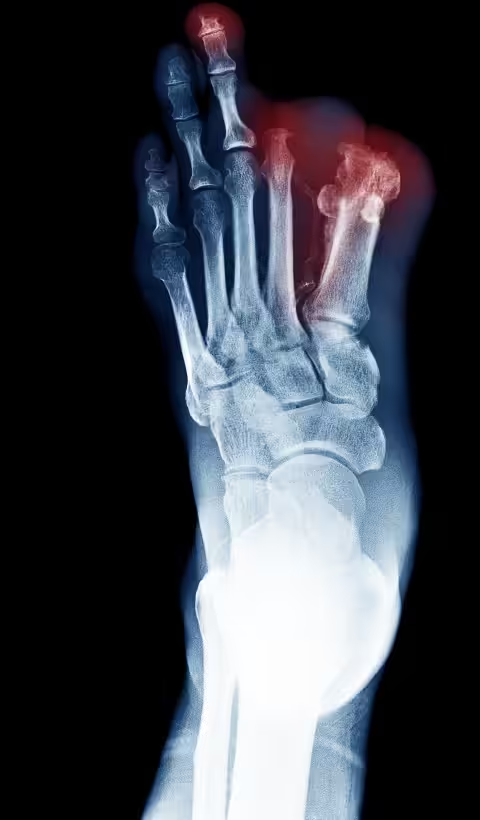
Osteomyelitis is infection of bone—in the foot, it most commonly develops through contiguous spread from an overlying soft tissue infection or wound (contiguous osteomyelitis) rather than hematogenous (blood-borne) spread. In patients with diabetes and peripheral neuropathy, foot wounds—particularly plantar ulcers—can penetrate to underlying bone. When bone is exposed in a wound (the “probe-to-bone” test is positive—a sterile metal probe inserted into the wound directly contacts bone), osteomyelitis is present until proven otherwise. Diabetic foot osteomyelitis is one of the most common reasons for lower extremity amputation and requires aggressive, systematic management.
Diagnosis
Diagnosing foot osteomyelitis requires combining clinical findings with imaging. Plain X-rays may show bone destruction, periosteal reaction, or sequestrum formation, but these changes take 2–4 weeks to appear; normal X-ray does not rule out early osteomyelitis. MRI is the most sensitive and specific imaging modality for osteomyelitis—it shows bone marrow edema and enhancement from early infection, and can delineate the extent of soft tissue involvement. Nuclear medicine bone scans and labeled white cell scans are alternatives when MRI is unavailable or contraindicated. Definitive diagnosis requires bone biopsy with culture to identify the causative organism and guide targeted antibiotic therapy; empirical treatment without culture data risks inadequate or inappropriate antibiotic selection.
Treatment
Antibiotic Therapy
Chronic foot osteomyelitis requires prolonged antibiotic therapy—typically 6 weeks of targeted antibiotics based on bone biopsy culture results. Staphylococcus aureus (including MRSA) is the most common causative organism; polymicrobial infections are common in diabetic foot osteomyelitis. IV antibiotics are often used initially, transitioning to oral bioavailable agents (fluoroquinolones, trimethoprim-sulfamethoxazole for MRSA, linezolid) when susceptibilities allow. Infectious disease consultation is essential for complex cases. Medical management without surgical debridement has increasing evidence for selected cases of diabetic foot osteomyelitis—particularly when the bone is accessible, the wound is being aggressively managed, and perfusion is adequate.
Surgical Debridement
Surgical debridement of infected bone (sequestrectomy or resection of infected cortical and cancellous bone) removes the nidus of infection, allows better antibiotic penetration, and is often necessary for definitive cure. Resection must achieve adequate margins—bone biopsy at the margins confirms that residual infection is not left behind. For osteomyelitis of the metatarsal or toe bones in diabetic patients, a minor amputation (digital or partial ray amputation) removes the infected bone with simultaneous wound management. The extent of resection must balance infection control with preservation of functional foot architecture—more extensive resection increases the risk of biomechanical complications and adjacent site breakdown.
Frequently Asked Questions
Can foot osteomyelitis be cured without surgery?
Some cases of foot osteomyelitis can be cured with antibiotics alone, particularly when the infection is early, the causative organism is susceptible to highly bioavailable oral antibiotics, the overlying wound can be closed or managed aggressively, and vascular supply is adequate for antibiotic delivery. Prospective studies in diabetic foot osteomyelitis have shown comparable outcomes between medical and surgical management in selected patients. However, many cases—particularly chronic osteomyelitis with sequestrum (dead bone) formation, osteomyelitis with inadequate vascular perfusion, or cases not responding to antibiotics after 2–4 weeks—require surgical debridement. The decision is made on an individual basis by the podiatric team, often in collaboration with infectious disease and vascular specialists.
What are the signs of osteomyelitis in the foot?
Classic signs of foot osteomyelitis include a non-healing wound overlying bone (particularly on the plantar foot), with or without bone visible or palpable in the wound base (probe-to-bone positive). Local signs include deep-tissue erythema, swelling, warmth, and purulent drainage that does not improve with superficial wound care and oral antibiotics. A sausage-shaped toe (diffuse swelling of a digit) is highly suggestive of underlying phalangeal osteomyelitis. Systemic signs (fever, elevated white blood cell count, elevated C-reactive protein and ESR) support active infection. Notably, many diabetic patients with osteomyelitis lack classic inflammatory signs due to neuropathy and impaired immune response—a non-healing wound lasting more than 2 weeks should raise suspicion for osteomyelitis regardless of local signs.
Is osteomyelitis life-threatening?
Foot osteomyelitis itself is rarely directly life-threatening in otherwise healthy individuals, but it is limb-threatening and can become life-threatening in high-risk patients. In diabetic patients and those with peripheral arterial disease, inadequately treated osteomyelitis can progress to deep soft tissue infection, ascending infection, and sepsis. In immunocompromised patients, the infection may spread to adjacent structures. The primary risk is loss of the limb through progressive infection requiring extensive amputation. Diabetic patients have a 14–24% lifetime risk of foot ulceration, and osteomyelitis developing from ulceration is a major driver of lower extremity amputation. Early aggressive management of diabetic foot wounds—before osteomyelitis develops—is the most effective prevention.
Medical References & Sources
- PubMed Research — Diabetic Foot Osteomyelitis
- Infectious Diseases Society of America — Diabetic Foot Infection Guidelines
- PubMed Research — Medical vs Surgical Osteomyelitis Treatment
Dr. Tom Biernacki, DPM is a board-certified podiatric surgeon at Balance Foot & Ankle in Howell and Bloomfield Township, Michigan. He manages diabetic foot infections, osteomyelitis, and wound care with antibiotic coordination, surgical debridement, and limb-salvage strategies.
Join 950,000+ Learning About Foot Health
Dr. Tom shares honest medical advice, supplement reviews, and treatment guides you won’t find anywhere else.
Subscribe on YouTube →📍 Located in Michigan?
Our board-certified podiatrists treat this condition at two convenient locations. Book online 24/7 at either office.
Insurance Accepted
BCBS · Medicare · Aetna · Cigna · United Healthcare · HAP · Priority Health · Humana · View All →
Howell Office
4330 E Grand River Ave
Howell, MI 48843
Get Directions →
Bloomfield Township Office
43494 Woodward Ave, #208
Bloomfield Township, MI 48302
Get Directions →
Pros & Cons of Conservative Care for foot care
Advantages
- ✓ Conservative care first
- ✓ Book online 24/7
- ✓ Multiple insurance accepted
Considerations
- ✗ Self-treatment can mask issues
- ✗ See a podiatrist if pain >2 weeks
Dr. Tom’s Recommended Products for foot care
Affiliate disclosure: As an Amazon Associate, Balance Foot & Ankle earns from qualifying purchases. We only recommend products we use with patients.
Footnanny Heel Cream Dr. Tom’s Pick
Best for: Daily moisturizer for cracked heels
Ready to Get Back on Your Feet?
Appointments in Howell + Bloomfield Township. Most insurance accepted. Dr. Tom Biernacki, DPM & team.
Call Now: (810) 206-1402
In-Office Treatment at Balance Foot & Ankle
If home treatment isn’t providing relief for your foot and ankle conditions, our podiatry team at Balance Foot & Ankle can help with expert evaluations and advanced in-office care.
Book online 24/7. (810) 206-1402
Related Conditions
Ready for Expert Care?
Appointments in Howell & Bloomfield Township, MI.
4.9★ | 1,200+ Reviews | 3,000+ Surgeries
Or call: (810) 206-1402
