
Quick answer: Walking Boot Fracture affects roughly 1 in 4 adults in our practice. Effective treatment starts with a targeted diagnosis, conservative-first treatment, and escalation only when needed. We treat this regularly at our Howell and Bloomfield Township practices. Call (810) 206-1402.
Medically reviewed by Dr. Tom Biernacki, DPM · Board-Certified Podiatric Surgeon · Last reviewed: April 2026 · Editorial Policy
In This Article
- Why a Walking Boot Is Prescribed for Foot and Ankle Fractures
- Fractures and Conditions Commonly Treated with a Walking Boot
- How Long Will I Need the Boot?
- Proper Walking Boot Use
- Transitioning Out of the Boot
- More Podiatrist-Recommended Foot Health Essentials
- Frequently Asked Questions
- In-Office Treatment at Balance Foot & Ankle
- Pros & Cons of Conservative Care for foot care
- Dr. Tom’s Recommended Products for foot care
Related Conditions
Medically reviewed by Dr. Tom Biernacki, DPM — Board-Certified Podiatric Surgeon — Balance Foot & Ankle, Howell & Bloomfield Township, MI. Last updated April 2026.
Why a Walking Boot Is Prescribed for Foot and Ankle Fractures
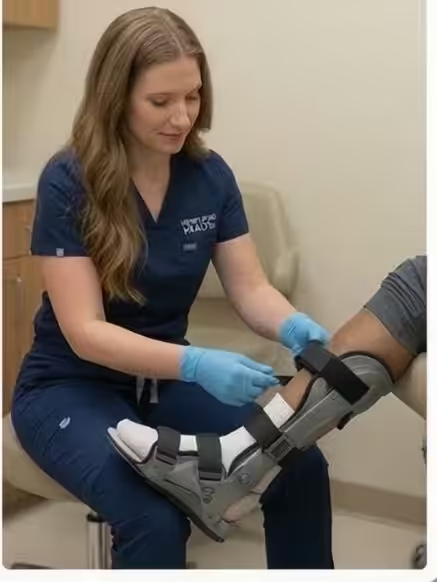

A walking boot (also called a cam boot, orthopedic boot, or fracture boot) is a removable rigid immobilization device prescribed for foot and ankle fractures, ligament injuries, and tendon conditions that require protection but not complete non-weight-bearing. Unlike a plaster cast, a walking boot can be removed for bathing, sleeping, and skin inspection—making it more practical for many patients. The boot provides controlled ankle and foot motion (or complete rigidity in some models), protects the fracture from excessive forces during walking, and allows enough stability for most patients to walk with minimal or no assistive devices.
Fractures and Conditions Commonly Treated with a Walking Boot
Walking boots are prescribed for a many foot and ankle conditions. Fractures commonly managed in a boot include: non-displaced fifth metatarsal fractures (both avulsion and Jones fractures in appropriate cases), second through fourth metatarsal fractures without significant displacement, stable ankle fractures (isolated lateral malleolus fractures or undisplaced medial malleolus fractures), toe and phalangeal fractures requiring more support than buddy taping, and stress fractures of the metatarsals and distal fibula. Non-fracture conditions managed in boots include severe ankle sprains (Grade III), plantar fasciitis refractory to conservative care, Achilles tendinopathy, and peroneal or posterior tibial tendon injuries.
How Long Will I Need the Boot?
Walking boot duration depends on the specific injury and healing rate. Most metatarsal stress fractures and non-displaced metatarsal fractures require 4–6 weeks in the boot. Ankle fractures typically require 6–8 weeks. Jones fractures of the fifth metatarsal (zone 2, at the metatarsal base) are notoriously slow-healing due to poor blood supply—they may require 6–10 weeks in a boot and have high non-union rates, which is why some surgeons recommend early surgical fixation for athletes and active patients. Ligament injuries (severe ankle sprains) typically require 4–6 weeks of boot use. Your podiatrist will monitor healing with X-rays every 3–4 weeks and determine when boot discontinuation is appropriate based on imaging and clinical examination.
Proper Walking Boot Use
A walking boot is only effective if worn consistently during all weight-bearing activity. The most common reason for delayed healing or re-injury is non-compliance—removing the boot too frequently during walking because it is uncomfortable. The boot should be worn during all standing and walking; it may be removed for bathing, sleeping, and wound care (if applicable). When walking in the boot, use an even gait—the rocker sole of the boot replaces normal ankle motion to support walking. If the boot creates significant leg length discrepancy (the booted leg is taller), a heel lift or shoe platform on the opposite shoe reduces back, hip, and knee discomfort from asymmetric height.
Keep the liner clean by washing it separately when the boot is removed. Apply a clean sock before wearing the boot to protect skin. Check the skin daily for pressure areas, blisters, or redness—adjust straps or add padding to relieve pressure points. Do not walk on unstable surfaces (wet floors, gravel) without additional caution, as the boot reduces ankle proprioception and increases fall risk.
Transitioning Out of the Boot
Transitioning from a walking boot to normal footwear is gradual, not immediate. After boot discontinuation, supportive athletic shoes with cushioned soles replace the boot for a further 2–4 weeks. Stiff dress shoes, heels, or flat unsupportive shoes should be avoided immediately after boot removal. Physical therapy begins at or shortly before boot discontinuation to address range-of-motion loss, strength deficits, and proprioception impairment that accumulate during immobilization. Most patients experience some muscle atrophy and stiffness after extended boot use—this is normal and resolves with rehabilitation.
More Podiatrist-Recommended Foot Health Essentials
Hoka Clifton 10

Max-cushion everyday shoe — podiatrist favorite for walking and running.

OOFOS Recovery Slide

Impact-absorbing recovery sandal — wear after long days on your feet.
As an Amazon Associate, Balance Foot & Ankle earns from qualifying purchases. Product recommendations are based on clinical experience; prices and availability shown above update live from Amazon.

When to See a Podiatrist
If foot or ankle pain has been bothering you for more than a few weeks, home care alone may not be enough. Balance Foot & Ankle offers online booking 24/7 at our Howell and Bloomfield Township clinics — no referral needed in most cases. Bring your current shoes and a short list of symptoms and we’ll build you a treatment plan in one visit.
Call Balance Foot & Ankle: (810) 206-1402 · Book online · Offices in Howell & Bloomfield Township
Frequently Asked Questions
Can I drive with a walking boot on my right foot?
Driving with a walking boot on the right foot is generally unsafe and not recommended. The boot significantly alters brake pedal feel and reaction time—studies have shown braking reaction time is impaired by a right-foot walking boot to a degree comparable to significant intoxication. Most podiatrists advise patients with right-foot boots not to drive until the boot is discontinued or, at minimum, until cleared by their provider. Patients with left-foot walking boots can drive automatic transmission vehicles safely (using the left foot is not involved in normal automatic driving). If driving is essential, discuss with your podiatrist whether the injury permits safe transfer to a temporary left-foot driving modification or whether ride-sharing is a more appropriate option during treatment.
How do I sleep with a walking boot?
Most podiatrists allow patients to remove the walking boot for sleep, as long as the patient is not weight-bearing at night (not getting up and walking in the dark without the boot). Sleeping without the boot is more comfortable and reduces skin moisture buildup. When sleeping with the boot off, place it within easy reach so it can be donned before standing. Elevating the foot on a pillow while sleeping reduces nighttime swelling. If your podiatrist has specifically instructed you to sleep in the boot (some fracture patterns require 24-hour immobilization), follow that instruction—ask for clarification if uncertain whether nighttime removal is permitted for your specific injury.
My fracture boot is causing knee and hip pain—is this normal?
Yes—knee, hip, and lower back pain from a walking boot is extremely common and results from two causes: the leg length discrepancy created by the boot’s sole thickness, and the altered gait mechanics that result from the rigid boot rocker sole. The height discrepancy causes pelvic tilt and spine asymmetry with every step, stressing the hip and lumbar spine. The solution is a shoe lift (sold at pharmacies) or an elevated insole for the opposite shoe to equalize leg lengths. Many podiatry practices provide a complementary lift with the boot prescription. If knee or hip pain is severe, physical therapy can address gait abnormalities. Informing your podiatrist allows them to confirm the boot fit and recommend appropriate accommodations.
VitaMedica Arnica Gel
Arnica gel plus 15 plant compounds for sore feet, plantar fasciitis flares and post-activity soreness. Apply a thin layer to the sore area.
Shop VitaMedica Arnica Gel →Medical References & Sources
- PubMed Research — CAM Boot Fracture Treatment Outcomes
- PubMed Research — Driving Safety with Walking Boot
- American Orthopaedic Foot & Ankle Society — Fracture Boots
Dr. Tom Biernacki, DPM is a board-certified podiatric surgeon at Balance Foot & Ankle in Howell and Bloomfield Township, Michigan. He treats foot and ankle fractures with walking boots, total contact casts, and surgical fixation, and guides patients through the full recovery process.
Join 950,000+ Learning About Foot Health
Dr. Tom shares honest medical advice, supplement reviews, and treatment guides you won’t find anywhere else.
Subscribe on YouTube →📍 Located in Michigan?
Our board-certified podiatrists treat this condition at two convenient locations. Book online 24/7 at either office.
Medically Reviewed by: Dr. Tom Biernacki, DPM — Board-Certified Podiatrist, Balance Foot & Ankle Specialists
📋 Dr. Tom Also Recommends
Podiatrist Recommended Orthotics 2026: Dr. Tom’s Top 10 Insoles & Arch Supports
A podiatrist’s complete clinical guide to the best insoles — custom orthotics, OTC picks, and what actually works for plantar fasciitis, flat feet, neuropathy & more.
Read the Full Guide →Insurance Accepted
BCBS · Medicare · Aetna · Cigna · United Healthcare · HAP · Priority Health · Humana · View All →
Howell Office
4330 E Grand River Ave
Howell, MI 48843
Get Directions →
Bloomfield Township Office
43494 Woodward Ave, #208
Bloomfield Township, MI 48302
Get Directions →
In-Office Treatment at Balance Foot & Ankle
When conservative care isn’t enough, Dr. Tom Biernacki and the team at Balance Foot & Ankle offer advanced treatment options — including Walking Boot Guide (CAM Boots) at our Howell and Bloomfield Township clinics.
Book online 24/7. Call (810) 206-1402 or book online.
Pros & Cons of Conservative Care for foot care
Advantages
- ✓ Conservative care first
- ✓ Book online 24/7
- ✓ Multiple insurance accepted
Considerations
- ✗ Self-treatment can mask issues
- ✗ See a podiatrist if pain >2 weeks
Dr. Tom’s Recommended Products for foot care
Affiliate disclosure: As an Amazon Associate, Balance Foot & Ankle earns from qualifying purchases. We only recommend products we use with patients.
Footnanny Heel Cream Dr. Tom’s Pick
Best for: Daily moisturizer for cracked heels
Ready to Get Back on Your Feet?
Appointments in Howell + Bloomfield Township. Most insurance accepted. Dr. Tom Biernacki, DPM & team.
Call Now: (810) 206-1402
Ready to feel better?
Appointments available in Howell and Bloomfield Township, Michigan.
Book Your VisitFrequently Asked Questions
What injuries require a walking boot?
Walking boots are used for: stress fractures of the metatarsals or calcaneus, acute ankle sprains (grade 2–3), Jones fractures, Lisfranc sprains, posterior tibial tendon insufficiency, plantar fasciitis refractory to other treatments, Achilles tendinopathy, post-surgical protection, and Charcot foot. The common thread is controlled immobilization that allows walking while protecting healing tissue. Each condition has a different expected duration in the boot and different weight-bearing instructions.
How long do I have to wear a walking boot?
Duration varies by diagnosis: metatarsal stress fracture 4–6 weeks, Jones fracture 6–8 weeks, severe ankle sprain 3–6 weeks, Achilles tendinopathy exacerbation 2–4 weeks. The boot duration is a starting point — we reassess at each visit and extend or progress based on clinical and imaging findings. Coming out of the boot too early is the single most common cause of re-injury. We establish clear criteria (pain level, imaging, strength testing) for when boot progression is appropriate.
Should I wear the walking boot all day, including when sleeping?
For most fractures: yes, including sleeping, for the first 2–4 weeks. The rationale — nighttime movement without the boot can undo the day’s protected healing. Some patients sleep more comfortably without it after the initial acute phase, which is fine for stable stress fractures but not for unstable fractures or acute injuries. We’ll give you specific sleeping instructions based on your injury. If not told otherwise, wearing it to bed is always the safer default.
Can I drive with a walking boot on my right foot?
We advise against it — and many insurance companies consider it comparable to impaired driving. A boot on the right foot significantly slows braking reaction time. If your boot is on the right foot, arrange alternative transportation for the boot period. Left-foot boots don’t affect driving mechanics in most vehicles. Automatic transmission cars with a left-foot boot are generally manageable; standard transmission is more complex. When in doubt, don’t drive — your safety and legal liability are at stake.
What is an Aircast boot vs. a standard walking boot?
Aircast and similar air-bladder boots (CAM walkers) allow inflation around the ankle for customizable compression and stability — particularly useful for ankle sprains and soft tissue injuries where swelling fluctuates. Standard rigid boots offer fixed immobilization more appropriate for fractures requiring strict positional control. We select the boot type based on injury mechanism and healing requirements. For most fractures, a rigid CAM boot is standard; for ankle ligament injuries, an air stirrup design is often preferred.
Will I lose muscle while wearing a walking boot?
Yes — disuse atrophy begins within 48–72 hours of immobilization. Calf muscle volume can decrease 3–5% per week in a boot. This is normal and expected. Upper-body workouts, swimming, and seated exercises maintain cardiovascular fitness during boot wear. After boot removal, a structured rehabilitation protocol (typically 4–8 weeks of progressive calf loading and balance training) rebuilds strength. Patients who do formal physical therapy post-boot return to full function 4–6 weeks faster than those who just stop wearing the boot.
How do I keep my other leg and back from hurting while in a boot?
The boot’s heel height (typically 3–4cm) creates a limb length discrepancy that stresses the opposite knee, hip, and lower back. Two solutions: (1) Use a boot with a rocker bottom sole to reduce gait compensation; (2) Add a heel lift to the opposite shoe to equalize leg lengths. Most patients who develop contralateral knee or back pain during boot wear benefit immediately from a 1–2cm heel lift in the non-booted shoe. We provide these at your boot fitting appointment.
What is a stress fracture and why does it need a boot?
A stress fracture is a micro-crack in bone caused by repetitive loading rather than acute trauma — common in the 2nd and 3rd metatarsals, calcaneus, and navicular in runners and active individuals. Unlike a full fracture, stress fractures don’t always show on X-ray initially; MRI is the gold standard diagnosis. The boot protects the healing fracture from the repetitive stress that caused it, allowing the micro-crack to fill in. Continuing to load an unprotected stress fracture risks complete fracture, which may require surgery.
Can I shower with a walking boot?
Most walking boots are not waterproof — the foam lining holds moisture, which softens skin and creates maceration risk. Remove the boot for showering, using a shower chair or crutches for balance if non-weight-bearing. Wrap the leg in a plastic bag secured above the knee for protection if needed. Completely dry the foot and liner before replacing. Some patients use a waterproof boot cover (DryPro) to shower with the boot on — acceptable for stable injuries but not for acute fractures where positioning matters.
When can I return to sports after using a walking boot?
Return-to-sport timing depends entirely on the diagnosis. For stress fractures: typically 4–8 weeks after X-ray or MRI confirms healing, then a graduated 4–6 week return-to-run program. For ankle sprains: functional testing (single-leg hop, agility) guides return rather than time alone. We use a structured protocol: walking → jogging → running → sports-specific drills → full return. There’s no universal timeline — we establish return criteria at your initial visit so you have a roadmap.
Get Expert Care at Balance Foot & Ankle
Appointments at our Howell and Bloomfield Township offices. Board-certified podiatric surgeons. Most insurance accepted.
Appointments in Howell & Bloomfield Township
Three board-certified podiatric surgeons. 1,200+ five-star reviews. Most insurance accepted.
Ready for Expert Care?
Appointments in Howell & Bloomfield Township, MI.
4.9★ | 1,200+ Reviews | 3,000+ Surgeries
Or call: (810) 206-1402

Dr. Tom Biernacki, DPM is a board-certified foot & ankle surgeon (ABFAS & ABPM) at Balance Foot & Ankle Specialists in Southeast Michigan. With over a decade of clinical experience, he specializes in heel pain, bunions, diabetic foot care, sports injuries, and minimally invasive surgery. Dr. Biernacki is a member of the APMA and ACFAS, and his patient education content on MichiganFootDoctors.com and YouTube has made him one of the most-followed foot & ankle educators on YouTube.